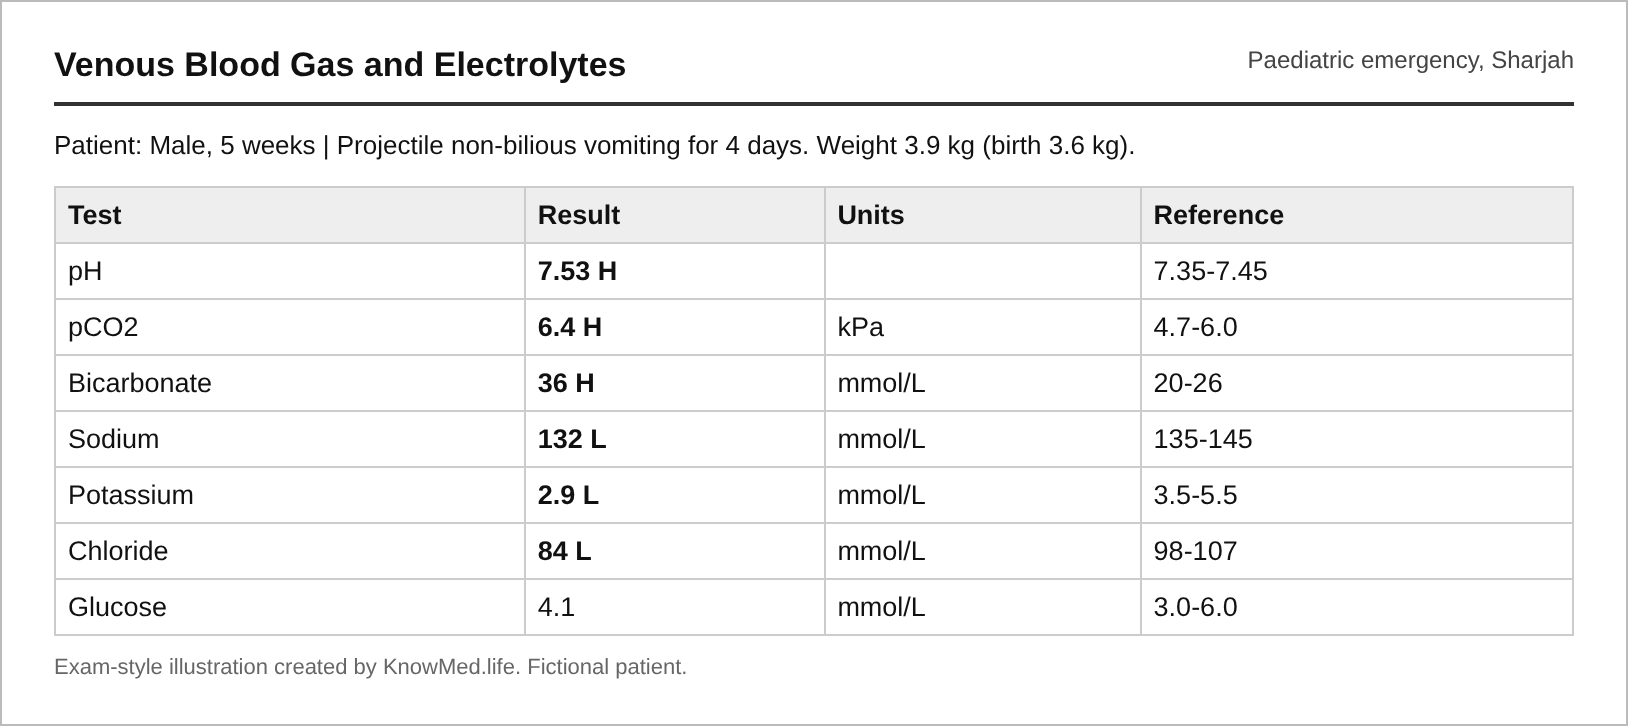
A 5-week-old first-born boy in Sharjah has had projectile non-bilious vomiting after every feed for 4 days and is hungry after vomiting. He is clinically dehydrated. A firm mass is felt in the right upper quadrant during a test feed. His venous blood gas is shown. What is the most appropriate next step?
Rationale
The gas shows a hypochloraemic, hypokalaemic metabolic alkalosis (pH 7.53, bicarbonate 36, chloride 84, potassium 2.9), typical of pyloric stenosis from loss of gastric acid with renal potassium wasting. Ultrasound confirms a thickened, elongated pylorus. Surgery (Ramstedt pyloromyotomy) is never an emergency: the alkalosis must be corrected first, because it raises the risk of postoperative apnoea. Surgery proceeds when chloride and bicarbonate are normal.
Why the other options are wrong:
- A. Operating with uncorrected alkalosis risks postoperative apnoea.
- B. He is dehydrated with a surgical condition.
- D. This is not reflux; medical treatment does not relieve the obstruction.
Where to revise: KnowMed library: "Hypertrophic Pyloric Stenosis" study PDF and MCQs