Free trial questions mapped to this clinical topic.
50 questionsSelf paced70% target score
Question 1
A GP in Dubai is assessing a 15-month-old girl with gastroenteritis. According to systematic review evidence, which combination of findings is most useful for detecting at least 5% dehydration?
Rationale
The JAMA rational clinical examination review (Steiner 2004) found that the three most useful individual signs for at least 5% dehydration are prolonged capillary refill time, abnormal skin turgor and an abnormal (deep, acidotic) respiratory pattern. No single sign is reliable on its own, so a combination of signs or a validated scale such as the Clinical Dehydration Scale should be used. Accurate pre-illness weight compared with current weight is the gold standard but is rarely available. NICE CG84 uses these and other features as red flags to separate clinical dehydration from shock. Parental history and dry mucosa are less specific because mouth-breathing and crying affect them.
Why the other options are wrong:
A. Tears, dry lips and parental report are subjective and much less accurate.
B. Thirst and fever are non-specific, and the fontanelle is closed in many toddlers.
C. Hypotension and weak pulses are late signs of decompensated shock; they are too insensitive to detect 5% dehydration.
Where to revise: Study PDF: "Dehydration in Children: Assess, Rehydrate, Re-feed" (KnowMed), page 4: Estimating severity: percent of body weight; page 7: Who needs blood and stool tests
A 58-year-old man with end-stage renal disease on haemodialysis for 6 years tells his nephrologist he wants to stop dialysis because of exhaustion and poor quality of life. He understands he will die within weeks. A capacity assessment confirms he has capacity and he is not depressed. His children beg the doctor to continue dialysis. What is the most appropriate action?
Rationale
A competent adult has the right to refuse any treatment, including life-sustaining treatment such as dialysis, even if the decision leads to death. Refusal by a competent patient is respected in both UAE practice and international ethics, because it expresses autonomy rather than an act of killing. The doctor should confirm capacity (which has been done), make sure the refusal is informed and voluntary, explore reversible factors such as depression or symptom burden, and document the discussion carefully. The patient should be offered renal palliative care for symptoms such as breathlessness, itch and agitation, and the family supported. He may change his mind at any time. The exam trap is letting the family overrule a competent patient.
Why the other options are wrong:
A. Relatives cannot override a competent adult's decision.
B. There is no legal basis to force treatment on a competent adult who refuses it.
C. Capacity has already been assessed and depression excluded; repeated referral delays respecting his wishes and is not required.
Where to revise: Study PDF: "End-of-Life Issues: Ethics, Law and UAE Practice" (KnowMed), page 4: Who decides? Capacity and surrogates; page 8: Withhold, withdraw, sedate, kill: what is legal?
A 34-year-old woman conceived by IVF with transfer of two embryos 23 days ago. She now has 6 hours of right iliac fossa pain. Pulse 96, BP 112/70. Her transvaginal ultrasound report is shown. Which statement about her diagnosis and management is correct?
Rationale
The scan shows a live intrauterine pregnancy together with a separate right adnexal ring- shaped mass containing a yolk sac and echogenic free fluid: a heterotopic pregnancy. It is rare after natural conception (about 1 in 10 000 to 30 000) but far more common after assisted reproduction, especially with multiple embryo transfer. Systemic methotrexate is contraindicated because it would harm the wanted intrauterine pregnancy. The usual treatment is laparoscopic salpingectomy, which preserves the intrauterine pregnancy in most cases; specialist alternatives include local potassium chloride injection into the ectopic sac. The free fluid suggests bleeding, so she needs prompt surgical review. The trap is the false reassurance that seeing an intrauterine pregnancy rules out an ectopic.
Why the other options are wrong:
A. Hyperstimulation can cause enlarged ovaries and fluid, but it does not produce a separate adnexal sac with a yolk sac.
B. After IVF, an intrauterine pregnancy does not exclude a coexisting ectopic.
D. Systemic methotrexate would harm the live intrauterine pregnancy.
Where to revise: Study PDF: "Ectopic Pregnancy: The Positive Test plus Pain Pathway" (KnowMed), page 13: Non-tubal sites and special situations - Same PDF, page 2: Implantation outside the endometrial cavity
A 70-year-old man is brought in after a rear-end collision at 40 km/h. He is alert (GCS 15), has no neurological deficit and has mild neck pain. He is wearing a collar. What is the most appropriate next step for his cervical spine according to the Canadian C-spine rule?
Rationale
The Canadian C-spine rule applies to alert, stable trauma patients. Any high-risk factor (age 65 or more, a dangerous mechanism, or paraesthesia in the limbs) mandates imaging regardless of other findings. At 70 years this man is high risk even after a simple rear-end collision, because degenerative spines fracture with low energy. In adults, CT is the first-line imaging test for the cervical spine (NICE NG41 and NG232), as it is more sensitive than plain films. Only patients with no high-risk factor and a low-risk factor (for example simple rear-end collision, sitting in the ED, ambulatory) proceed to the active rotation test of 45 degrees left and right. The exam trap is applying the low-risk rotation test before checking high-risk factors.
Why the other options are wrong:
B. The rotation test is used only when there are no high-risk factors; age 70 is a high-risk factor.
C. Clinical clearance without imaging is not allowed in a patient aged 65 or more under the Canadian rule.
D. Flexion-extension films are not first-line in acute trauma and are unsafe before excluding a fracture.
Where to revise: Study PDF: "Management of Trauma Patients: The xABCDE Pathway" (KnowMed), page 12: Head-to- toe, decision rules and missed injuries
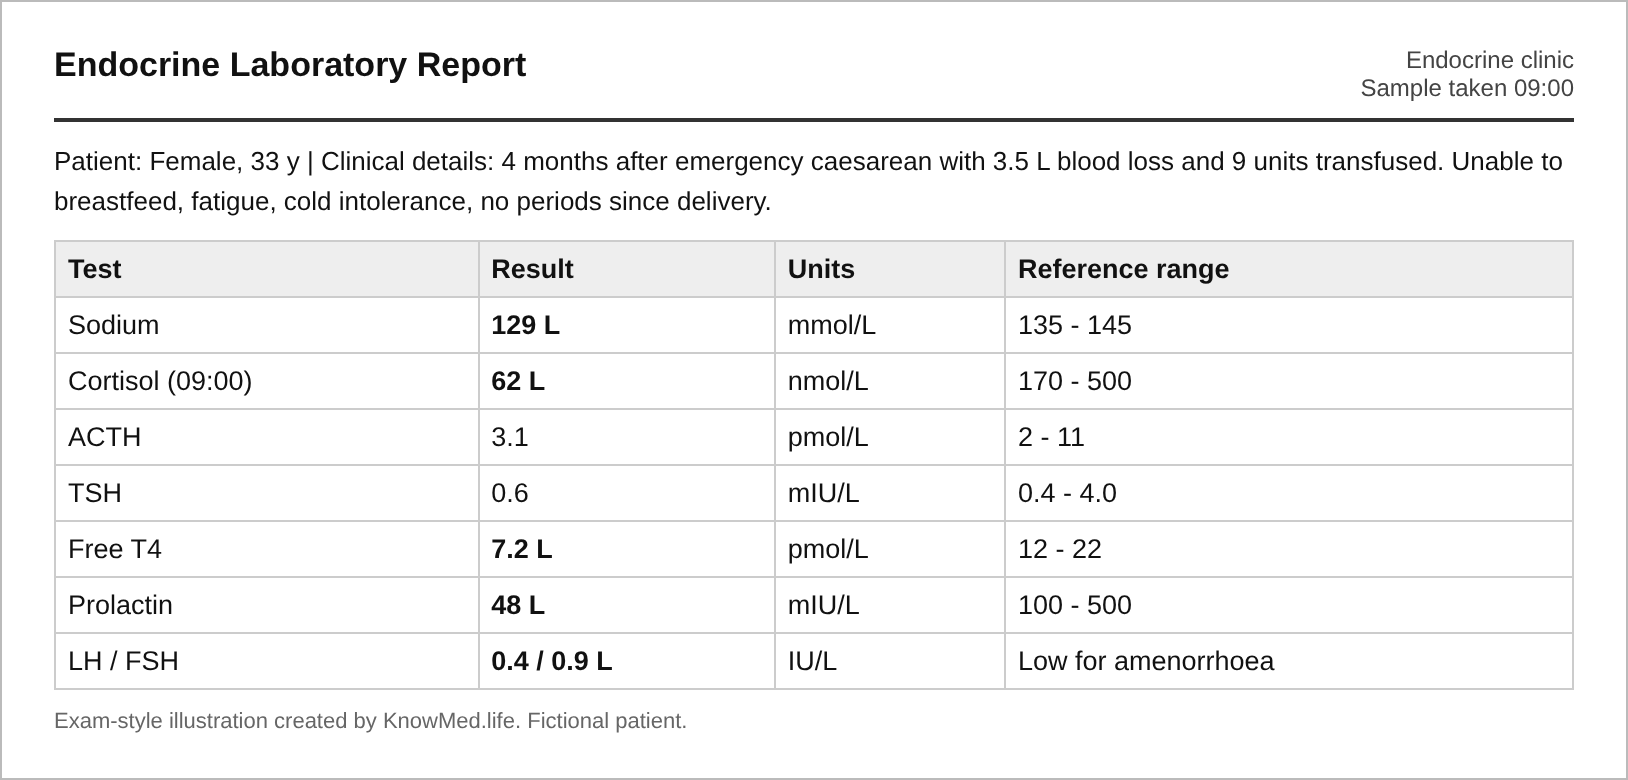
A 33-year-old woman is referred 4 months after a massive obstetric haemorrhage. Her symptoms and blood results are shown. Which treatment should be started first?
Rationale
Failure of lactation, amenorrhoea, fatigue and cold intolerance after a massive PPH suggest Sheehan syndrome: ischaemic necrosis of the pituitary, which enlarges in pregnancy and is vulnerable to hypotension. The results show secondary (central) hypoadrenalism with a low cortisol and an inappropriately normal ACTH, central hypothyroidism with a low free T4 and a normal TSH, low prolactin and low gonadotrophins. Hyponatraemia reflects cortisol deficiency. Glucocorticoid replacement must start before thyroxine, because thyroxine speeds cortisol clearance and can precipitate an adrenal crisis. Thyroxine and sex hormone replacement follow, and pituitary imaging and endocrine follow-up are arranged. Failure of lactation is classically the first sign.
Why the other options are wrong:
B. Starting levothyroxine before cortisol can trigger an adrenal crisis.
C. Oestrogen replacement is needed later but is not the first priority with hypoadrenalism.
D. Cabergoline lowers prolactin; her prolactin is already low.
Where to revise: Study PDF: "Postpartum Haemorrhage: The 4 Ts Emergency Pathway" (KnowMed), page 14: After the bleeding stops
In a trial of a new antihypertensive, 15% of patients randomised to the new drug stopped it because of side effects and some switched to the comparator. The investigators analysed every patient in the group to which they were originally randomised, whatever treatment they actually took. What is this approach called?
Rationale
In intention-to-treat (ITT) analysis, every participant is analysed in the group to which they were randomised, regardless of adherence, crossover or withdrawal. This preserves the balance of known and unknown confounders created by randomisation and reflects real-world effectiveness, because in practice some patients will stop a drug. ITT tends to bias results towards no difference (conservative), which is why it is the primary analysis for superiority trials. Per-protocol analysis includes only those who adhered to the allocated treatment; it may exaggerate benefit because non-adherent patients often differ systematically. Non-inferiority trials usually report both, because ITT can make two treatments look falsely similar.
Why the other options are wrong:
A. Per-protocol analysis excludes non-adherent patients.
B. As-treated analysis groups patients by the treatment actually received, breaking randomisation.
D. Subgroup analysis examines effects within defined subsets of patients.
Where to revise: Study PDF: "Interpreting Medical Evidence: From Abstract to Answer" (KnowMed), page 6: Is the trial valid?
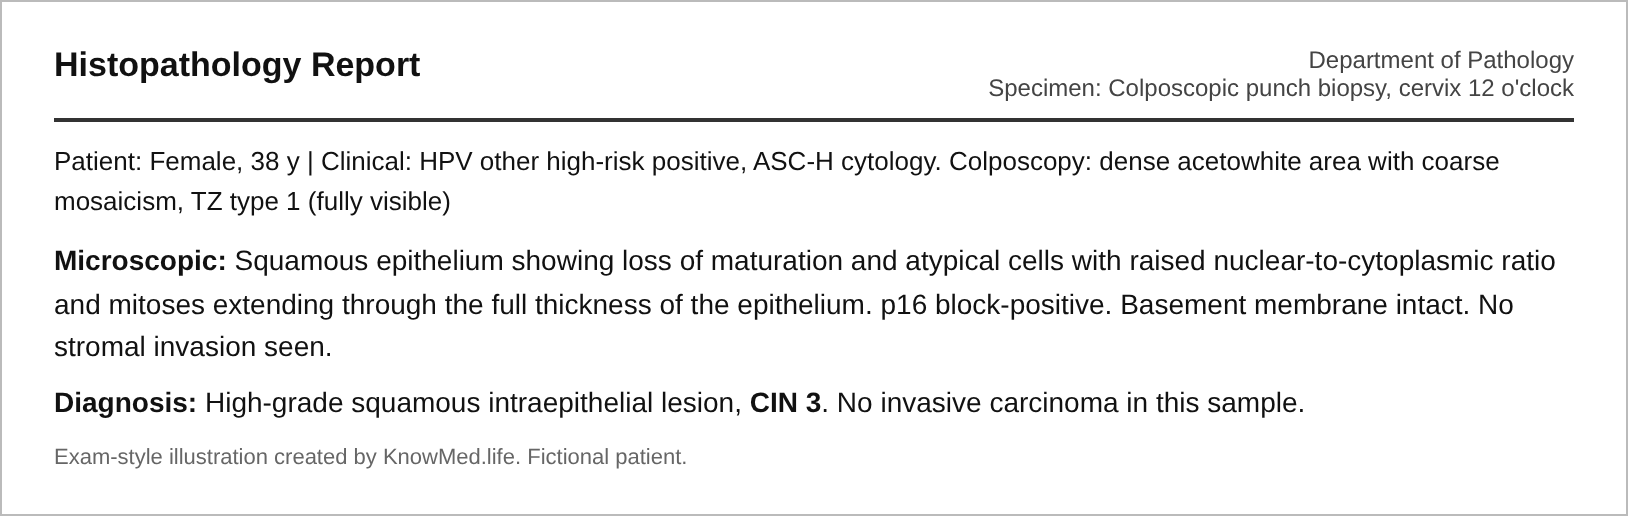
A 38-year-old woman undergoes colposcopy after an abnormal screen. The entire transformation zone was visible. Her biopsy report is shown. What is the most appropriate treatment?
Rationale
The biopsy shows full-thickness dysplasia with an intact basement membrane and p16 block positivity: CIN 3 (HSIL), with no invasion. CIN 3 has a substantial risk of progression to invasive cancer (about 30% over 30 years if untreated) and must be treated. LLETZ (LEEP) is the standard outpatient treatment under local anaesthetic; it removes the whole transformation zone and gives a specimen to confirm margins and exclude occult invasion. Follow-up is with HPV testing at 6 months regardless of margin status. Excision roughly doubles the risk of later preterm birth, which should be explained to women planning pregnancy.
Why the other options are wrong:
A. Observation is appropriate for CIN 1, and in selected young women with CIN 2, but never for CIN 3.
B. Imiquimod is not standard treatment for cervical CIN 3.
C. Hysterectomy is not first-line treatment for CIN and does not remove the need for vault follow-up.
Where to revise: Study PDF: "Cervical Cancer: Screen, Stage, Treat" (KnowMed), page 4: CIN and the Bethesda cytology language; page 9: See it, biopsy it, excise it
A 30-year-old woman at 31 weeks presents with tightenings. The midwife plans a fetal fibronectin test. Which of the following would make the result unreliable?
Rationale
Fetal fibronectin is a glycoprotein that 'glues' the fetal membranes to the decidua, and its leak into the cervicovaginal secretions after 22 weeks signals disruption of this interface. Semen, recent intercourse (within 24 hours), vaginal bleeding, lubricant gel, amniotic fluid and a prior digital examination can all cause false-positive results. The swab should therefore be taken from the posterior fornix during a sterile speculum examination before any digital examination. NICE recommends fibronectin from 30+0 weeks when transvaginal ultrasound is not available, with a threshold of 50 ng/mL. It should not be combined with cervical length testing to diagnose preterm labour.
Why the other options are wrong:
A. Sending a urine culture does not affect the cervicovaginal fibronectin result.
B. A normal CTG has no effect on fibronectin testing.
D. 31 weeks is within the gestation range where NICE recommends fibronectin testing (30+0 weeks or more).
Where to revise: Study PDF: "Preterm Labour and Birth: Diagnose, Delay, Protect" (KnowMed), page 6: Tests and their thresholds
A 30-year-old woman at 34 weeks of pregnancy has itching, mild discomfort and occasional bright red bleeding from prolapsing piles that she pushes back after defecation. She is constipated. There is no thrombosis. What is the most appropriate management?
Rationale
Haemorrhoids affect up to two-thirds of pregnant women, especially in the third trimester and after delivery, because of raised intra-abdominal pressure, progesterone-related constipation and increased venous volume. Management is conservative: fibre, fluids, a safe osmotic laxative (lactulose), warm sitz baths and short courses of topical agents; ASCRS states hydrocortisone and pramoxine are safe and effective in late pregnancy. Procedures are deferred until after delivery (AGA), because symptoms often settle postpartum, unless there is thrombosis or strangulation. Haemorrhoids are not an indication for caesarean section.
Why the other options are wrong:
B. Banding is deferred in pregnancy unless absolutely necessary.
C. Surgery in pregnancy is reserved for complications such as strangulation.
D. Haemorrhoids are not an indication for caesarean delivery.
Where to revise: Study PDF: "Haemorrhoids: Grade, Band, Excise" (KnowMed), page 13: Pregnancy, cirrhosis, IBD and anticoagulants; page 9: First-line care that works
A 35-year-old man asks about bowel screening. His father was diagnosed with colorectal cancer at age 52. No other relatives are affected and he has no symptoms. According to US multi-society guidance, what should he be advised?
Rationale
One first-degree relative diagnosed under age 60 doubles to triples the risk. US multi-society guidance advises colonoscopy starting at age 40, or 10 years before the youngest affected relative's age at diagnosis (whichever is earlier), repeated every 5 years. Here 52 minus 10 gives 42, so 40 is earlier. If the relative had been diagnosed at 60 or older, he would start at 40 with average-risk intervals. If the family history suggests Lynch syndrome (several relatives, young ages, endometrial cancer), refer for genetic assessment. A family history moves screening earlier and makes colonoscopy the test of choice.
Why the other options are wrong:
A. This is an average-risk programme that is too late for a high-risk relative.
B. CEA has no role in screening.
C. Waiting for symptoms defeats the purpose of screening a high-risk person.
Where to revise: Study PDF: "Colorectal Cancer: Detect, Stage, Cure" (KnowMed), page 9: Family history (US guidance)
A 29-year-old man with OCD and a chronic motor tic disorder has had no adequate response to two SSRIs at maximum tolerated doses for 12 weeks each, clomipramine, and 20 sessions of intensive ERP. After multidisciplinary review in a specialist OCD service, which is the most appropriate next pharmacological step?
Rationale
He has treatment-resistant OCD. NICE CG31 allows adding an antipsychotic to an SSRI or clomipramine after multidisciplinary review and full treatment trials, and MSD notes that atypical antipsychotics such as aripiprazole and risperidone have the strongest evidence for augmentation, with patients who have comorbid tics responding better. Augmentation should be started by specialists, not routinely in primary care, with metabolic monitoring. If there is still no response, specialist options include intensive or inpatient ERP and, for severe refractory cases, neuromodulation such as deep brain stimulation. Response should be reviewed after several weeks and the antipsychotic stopped if it does not help.
Why the other options are wrong:
A. Combining an MAOI with clomipramine or an SSRI can cause fatal serotonin syndrome; a washout of at least 2 weeks is required.
C. Benzodiazepines do not treat the core symptoms of OCD and risk dependence.
D. Stopping medication in severe refractory OCD risks marked deterioration; augmentation is recommended.
Where to revise: Study PDF: "Obsessive-Compulsive Disorder: Recognise, Expose, Treat" (KnowMed), page 12: Drug safety and refractory OCD; page 9: NICE CG31 stepped-care algorithm (adults)
A 58-year-old man with limited health literacy has just been started on basal insulin by a family physician. The doctor has explained how to inject, when to check glucose and how to recognise hypoglycaemia. What is the best way to confirm that he has understood?
Rationale
Teach-back asks the patient to explain or demonstrate, in his own words, what he has been told, and it reveals gaps that closed questions miss. It is framed as a check on the clinician's explanation ("to make sure I explained it clearly..."), so the patient does not feel tested. It is especially important with low health literacy, new high-risk medicines such as insulin, and language barriers. Any misunderstanding is re-explained and checked again. It sits within ask-tell-ask: ask what the patient knows, tell a chunk, then ask again. The trap is the closed question "Did you understand?", to which most patients say yes regardless.
Why the other options are wrong:
B. An open invitation for questions is useful but does not confirm understanding.
C. A yes or no question is often answered "yes" out of politeness or embarrassment.
D. Written material helps but cannot check understanding, particularly with low literacy.
Where to revise: Study PDF: "Communication During Residency: Breaking Bad News and Beyond" (KnowMed), page 6: Plans, prognosis and hope; page 14: Communication tools at a glance
A 45-year-old man presents 5 days after the onset of breathlessness with a complete collapse of the right lung. A chest drain is inserted and attached to high-pressure suction. One hour later he develops cough with pink frothy sputum, SpO2 falls to 86% and there are crackles over the right lung. What is the most likely diagnosis?
Rationale
Re-expansion pulmonary oedema occurs when a lung that has been collapsed for more than about 2-3 days is expanded rapidly, especially with suction. Increased capillary permeability and reperfusion injury of the chronically collapsed lung cause unilateral pulmonary oedema within hours, with cough, frothy sputum, hypoxia and crackles on the treated side. It is prevented by avoiding early high suction after a long-standing collapse and by draining large effusions slowly. Treatment is supportive: stop the suction, give oxygen and ventilatory support if needed. Most cases resolve within 24-72 hours, but it can be fatal.
Why the other options are wrong:
A. Tension pneumothorax gives absent breath sounds and hyper-resonance, not crackles with frothy sputum, and a functioning drain makes it unlikely.
C. Intraparenchymal placement causes bleeding or air leak, not unilateral crackles with frothy sputum after re-expansion.
D. Haemothorax causes dullness and blood in the drain, not pulmonary oedema.
Where to revise: Study PDF: "Pneumothorax: From Bleb to Tension" (KnowMed), page 12: Complications to anticipate; page 10: Chest drain: the safe triangle
A 9-year-old boy (32 kg) recovered from peanut anaphylaxis in an Emergency Department in Abu Dhabi and is ready for discharge. Which discharge plan follows NICE CG134 and RCUK guidance?
Rationale
After emergency treatment of anaphylaxis, NICE CG134 recommends that every patient is referred to a specialist allergy service and that those at risk of recurrence (such as food allergy) are offered adrenaline auto-injectors with hands-on training before discharge. Current UK guidance is to carry two auto-injectors at all times, because a second dose may be needed and devices can fail or be misused. At 32 kg he should receive the 0.3 mg device (0.15 mg devices are for about 15-30 kg). A written anaphylaxis emergency action plan, avoidance advice, an asthma review and a school plan complete the package. NICE also advises that children under 16 with anaphylaxis are admitted under the paediatric team.
Why the other options are wrong:
A. One device is not enough, and steroids do not prevent recurrence or biphasic reactions.
B. Antihistamines do not treat anaphylaxis, and allergy referral is mandatory, not optional.
D. Allergy testing should be done by a specialist service, ideally 4-6 weeks after the reaction, when tests are more reliable; testing too early may give false negatives.
Where to revise: Study PDF: "Anaphylaxis: Recognise, Adrenaline, Repeat" (KnowMed), page 12: How long to watch, and the discharge kit; page 8: IM adrenaline doses you must know by heart (auto-injectors)
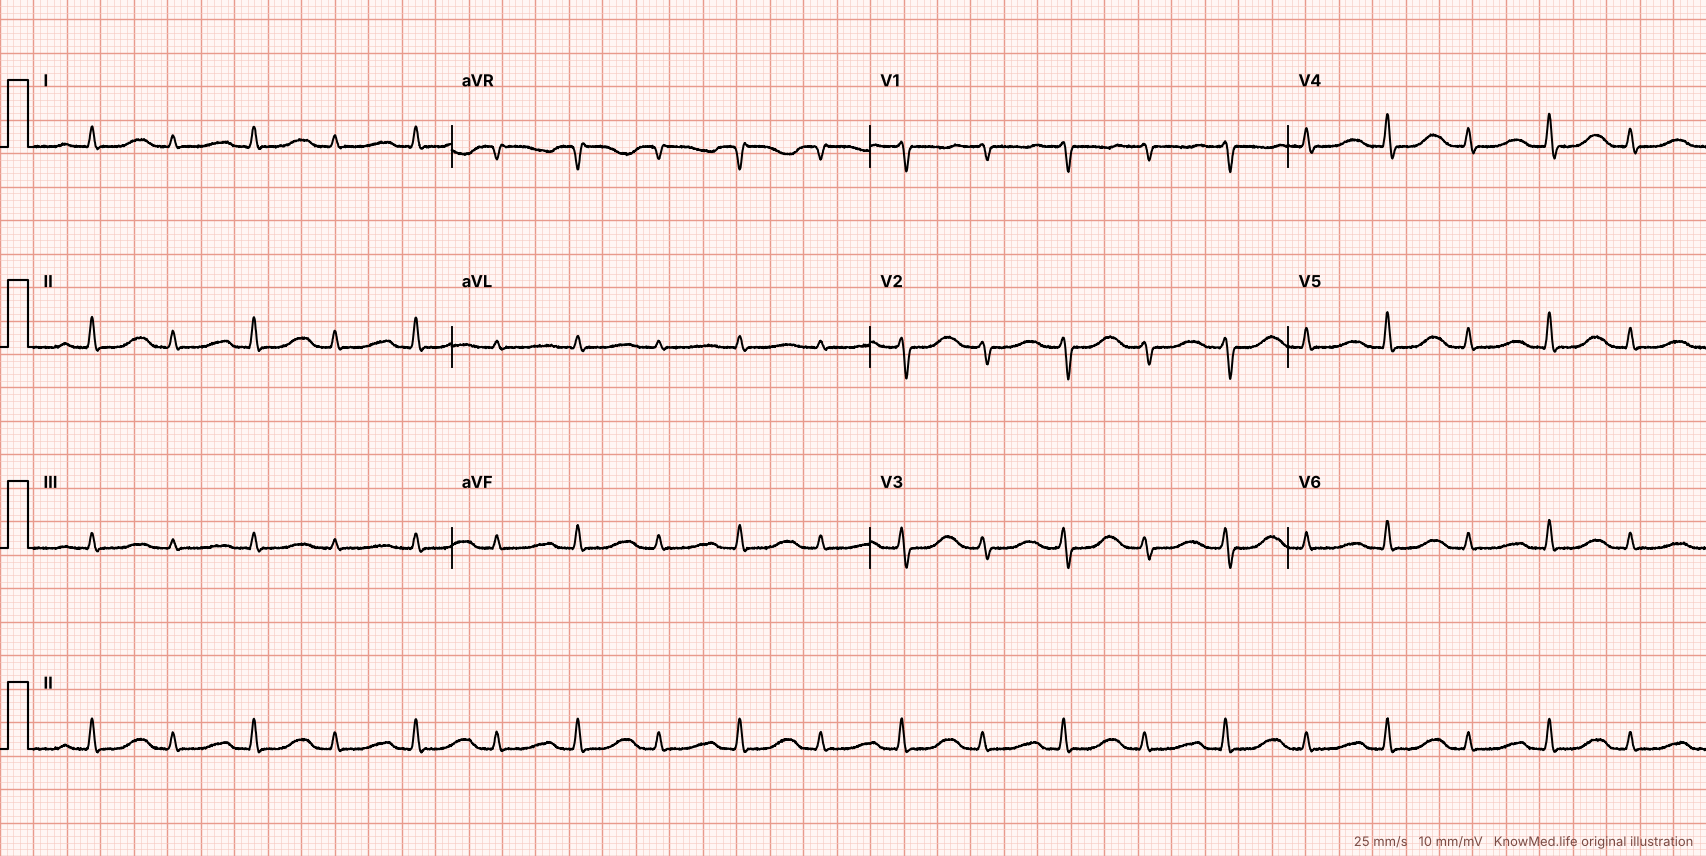
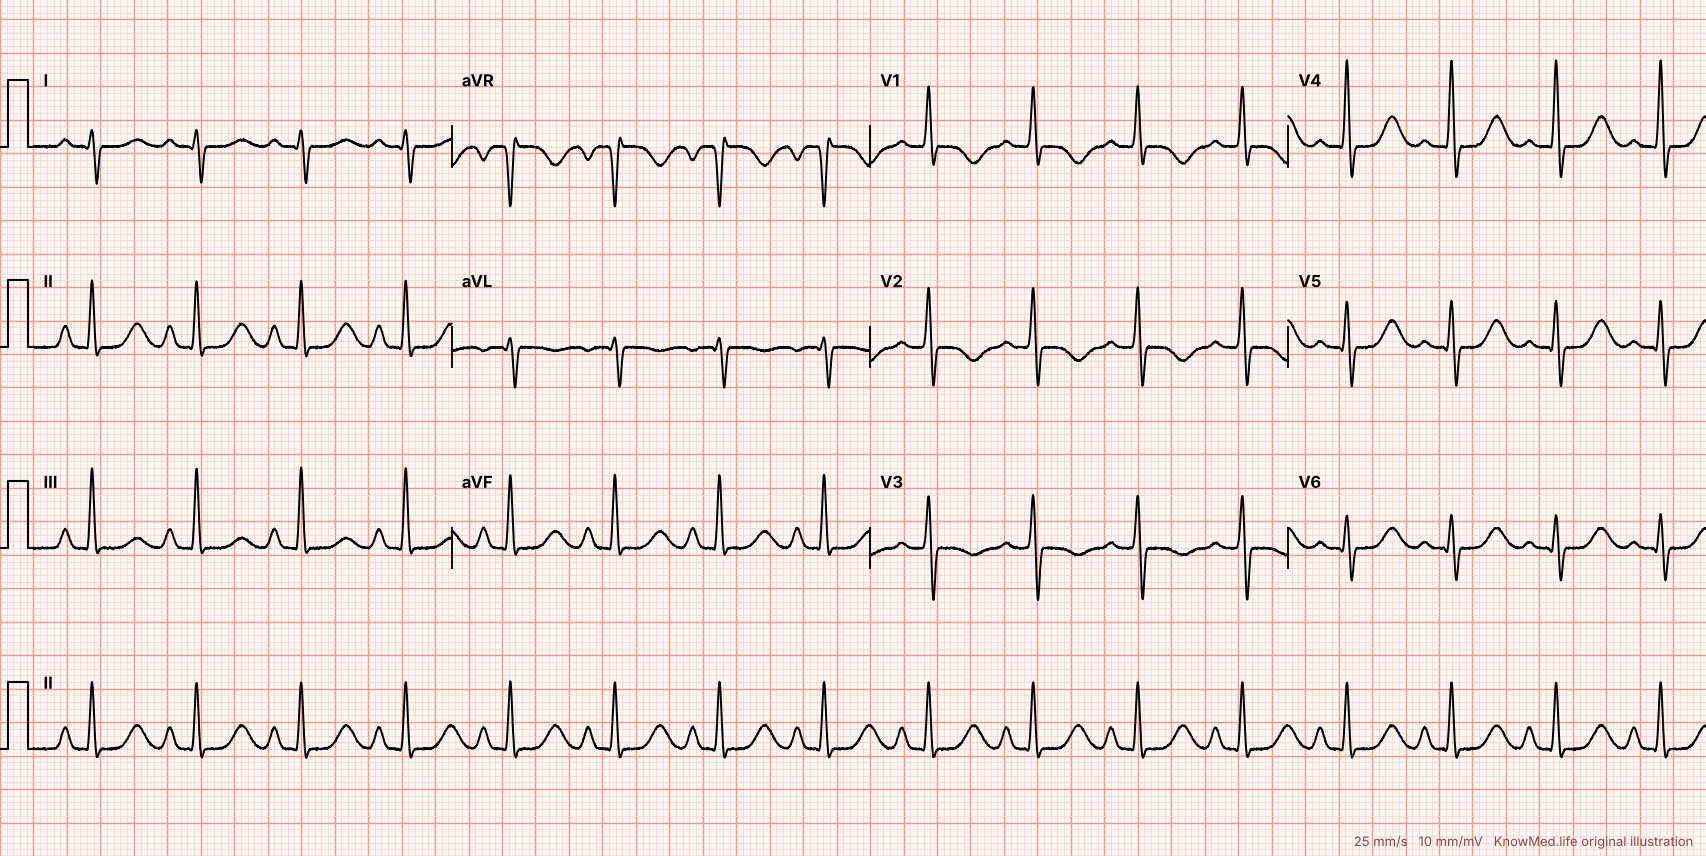
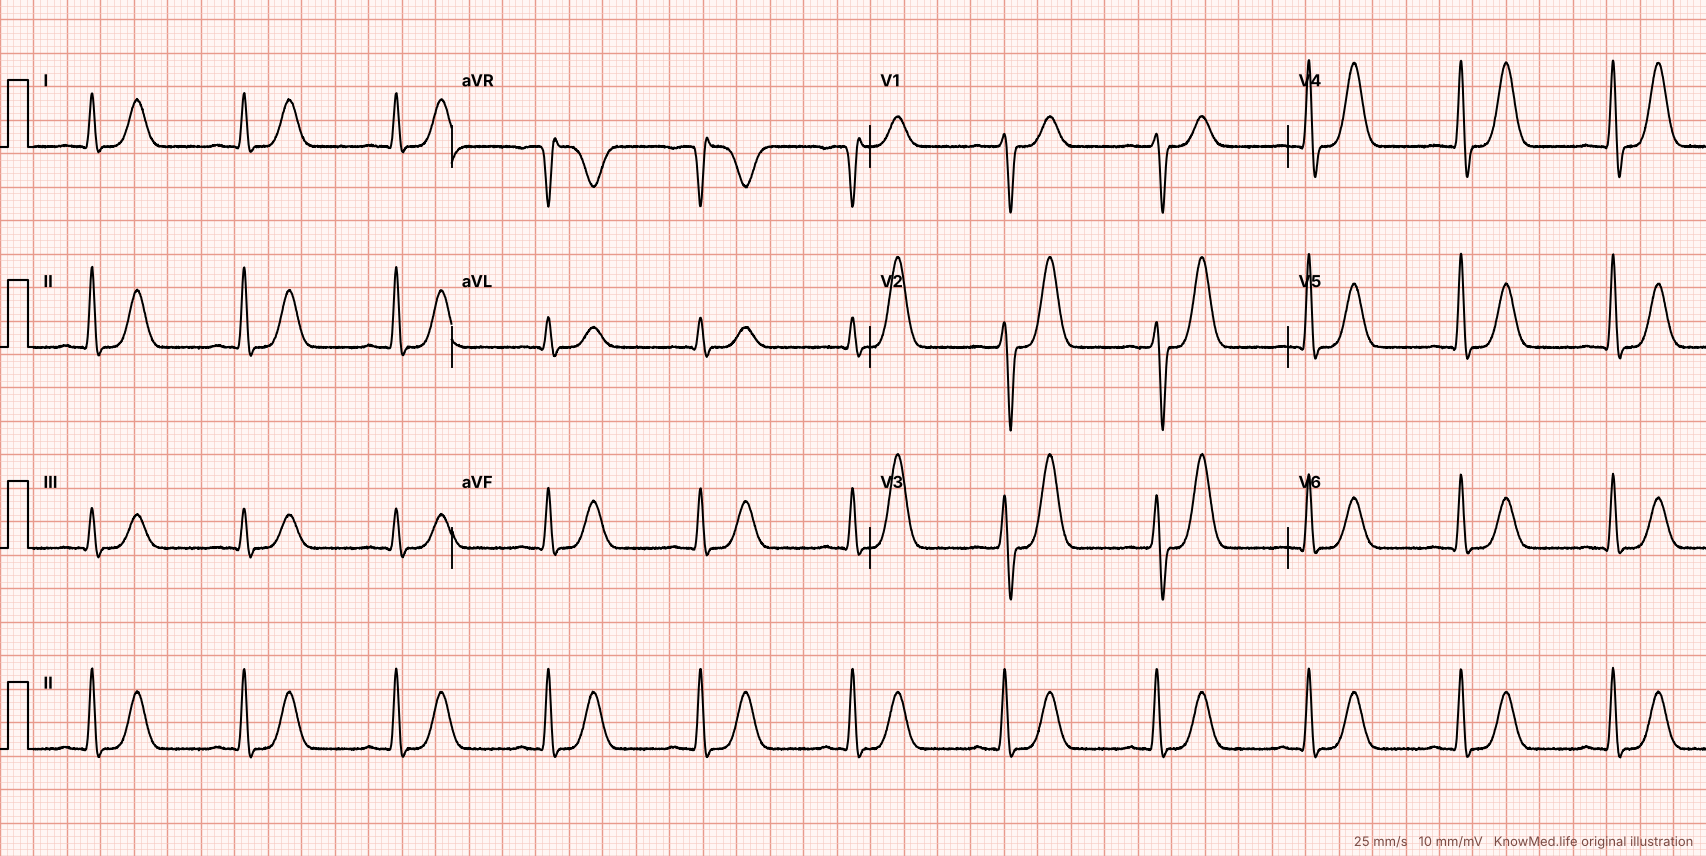
A 64-year-old woman with metastatic lung cancer has 1 week of increasing breathlessness. BP 92/70 mmHg, HR 124/min, JVP raised 8 cm, heart sounds quiet, chest clear. Her ECG is shown. What is the most likely diagnosis?
Rationale
The ECG shows sinus tachycardia, low QRS voltage in all leads, and electrical alternans (QRS amplitude alternating beat to beat, best seen in the rhythm strip and chest leads). Low voltage is caused by the insulating fluid around the heart, and alternans by the heart swinging within a large effusion. Together with hypotension, a raised JVP, quiet heart sounds and clear lungs in a patient with cancer, this is cardiac tamponade until proven otherwise. Malignancy is the commonest cause of large effusions and tamponade in adults. The next step is urgent bedside echo and pericardiocentesis; these ECG signs are specific but not sensitive, so a normal-voltage ECG does not exclude tamponade.
Why the other options are wrong:
B. Massive PE causes tachycardia and an RV strain pattern (S1Q3T3, right axis, T inversion V1-V4), not low voltage with alternans.
C. There is no ST elevation or Q waves to suggest MI.
D. Hypothyroidism causes low voltage but with bradycardia, not tachycardia, hypotension and alternans.
Where to revise: Study PDF: "Pericardial Effusion and Cardiac Tamponade: The Obstructive Shock Pathway" (KnowMed), page 6: ECG and chest X-ray; page 13: Cancer, TB, renal, thyroid
A 45-year-old man who smokes 25 cigarettes a day attends an RTA medical. When asked about smoking, he says he enjoys it and has no intention of stopping in the next 6 months. What is the most appropriate next step?
Rationale
In the stages of change model he is in precontemplation (no intention to change in the next 6 months). Every smoker should be asked, advised and assessed using the 5As (Ask, Advise, Assess, Assist, Arrange). For someone not yet ready, the evidence-based approach is brief, clear and personalised advice plus motivational interviewing to explore ambivalence and build motivation, leaving the door open for support. Once he moves to contemplation or preparation, combine behavioural support with pharmacotherapy (varenicline, combination NRT or bupropion), which roughly doubles to triples quit rates. Tobacco counselling for all adults is a USPSTF grade A recommendation and smoking cessation is the single most effective preventive action.
Why the other options are wrong:
A. Medication is effective when the patient is ready to set a quit date; prescribing in precontemplation rarely succeeds.
B. Coercion is unethical and damages the therapeutic relationship.
D. At 45 he is below the lung screening age of 50.
Where to revise: Study PDF: "Preventive Medicine: Prevent, Screen, Protect" (KnowMed), page 13: Counselling that prevents disease
A 3-week-old girl passed meconium at 60 hours and has had distension and infrequent stools. Her contrast enema report is shown. What is the most appropriate next investigation?
Rationale
Delayed passage of meconium beyond 48 hours in a term baby is the classic red flag for Hirschsprung disease. The enema shows a narrow rectum with a cone-shaped transition zone at the rectosigmoid junction, a rectosigmoid index below 1 and delayed contrast evacuation, which suggests short-segment aganglionosis. Imaging is suggestive but not diagnostic, and the transition zone may be absent in neonates or total colonic disease. The diagnosis must be confirmed histologically by rectal suction biopsy, which shows absent ganglion cells. Until then she should be watched closely for enterocolitis, and rectal washouts may be needed.
Why the other options are wrong:
B. A plain film adds little once the contrast study has been done and cannot confirm aganglionosis.
C. Thyroid tests are reasonable in some infants with constipation, but the imaging and history point strongly to Hirschsprung disease.
D. Colonoscopy does not sample the submucosa adequately and is not used to diagnose Hirschsprung disease.
Where to revise: Study PDF: "Constipation in Children and Adolescents: The Withholding Cycle" (KnowMed), page 5: Red flags that point away from functional; page 7: Test only when the story says so
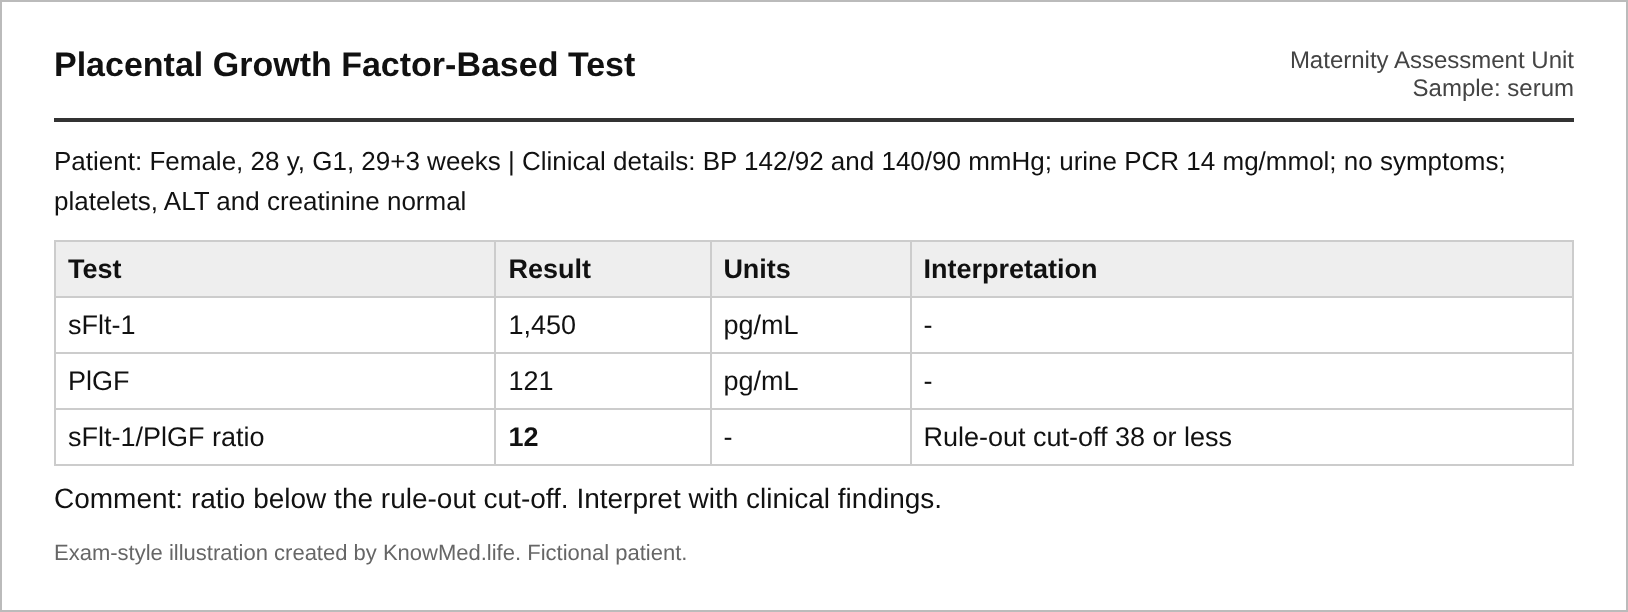
A 28-year-old woman at 29+3 weeks has new hypertension. She is asymptomatic and her other tests are normal. A placental growth factor-based test is performed and the result is shown. What is the best interpretation?
Rationale
She has new hypertension after 20 weeks (142/92 and 140/90 mmHg) with a uPCR of 14 mg/mmol and normal bloods, which is gestational hypertension. NICE DG49 recommends a PlGF-based test once, between 20 and 36+6 weeks, when pre-eclampsia is suspected. Pre-eclampsia is associated with a high anti-angiogenic sFlt-1 and a low PlGF; an sFlt-1/PlGF ratio of 38 or less (here 12) has a very high negative predictive value and rules out pre-eclampsia within the next week (PROGNOSIS study). She still needs treatment if BP stays above 140/90, weekly BP and urine checks, and repeat assessment if symptoms develop. About a quarter of women with gestational hypertension progress to pre-eclampsia, so surveillance continues. The trap is thinking the test diagnoses chronic hypertension or decides the timing of birth by itself.
Why the other options are wrong:
A. The low ratio argues against pre-eclampsia; there is no indication for delivery.
C. Hypertension arising after 20 weeks is gestational, not chronic, and needs monitoring.
D. PlGF-based tests are validated from 20 to 36+6 weeks, so the test is valid at 29 weeks.
Where to revise: Study PDF: "Hypertensive Pregnancy Disorders: From Gestational Hypertension to Eclampsia" (KnowMed), page 7: Assess the mother and the baby; page 2: Four hypertensive disorders of pregnancy
A term baby is born in Abu Dhabi on 15 October. His mother received the RSV vaccine (RSVpreF) at 33 weeks of gestation, 5 weeks before delivery. Which is correct regarding RSV prevention for the baby?
Rationale
The UAE schedule gives one dose of RSV long-acting monoclonal antibody at birth to babies born between 1 September and 1 March, unless the mother received the RSV vaccine in pregnancy. Maternal RSVpreF given at 32-36 weeks, at least 14 days before delivery, transfers protective antibody across the placenta. This baby was born 5 weeks after maternal vaccination, so he is protected and does not need the antibody. Exceptions where an infant may still receive it include delivery less than 14 days after maternal vaccination or certain high-risk conditions. Routine birth BCG and hepatitis B are still given.
Why the other options are wrong:
B. Both products are not needed for most infants; maternal vaccination given at least 14 days before birth is sufficient.
C. The antibody is given at birth or at the start of the season, not routinely with the 2-month vaccines, and is not needed here.
D. There is no RSV vaccine licensed for infants; infants receive monoclonal antibody, not vaccine.
Where to revise: Study PDF: "Immunization Schedule: Ages, Intervals, Catch-Up" (KnowMed), page 9: Preterm babies (RSV protection); page 13: Seasonal schedules: influenza and RSV
A 58-year-old widower with depression and alcohol use disorder attends his family physician in Sharjah for a repeat prescription. He lives alone, lost his job 6 months ago and took an overdose of his late wife's tablets 2 years ago. Which single factor in his history most strongly predicts a future completed suicide?
Rationale
A previous suicide attempt is the single strongest predictor of eventual death by suicide, and WHO lists it as the most important individual risk factor in the general population. This man has a cluster of other risk factors (male, older, widowed, living alone, unemployed, depression, alcohol), and these add to his risk, but none is as powerful as a past attempt. The risk after an attempt stays raised for years, which is why every attempt, even a remote one, must be recorded and asked about. Management here is to ask directly about current ideation, plan and intent, treat the depression and alcohol use, restrict access to means and arrange follow-up. The exam trap is choosing male sex because men die by suicide about 4 times more often than women; that is a population fact, not the strongest individual predictor.
Why the other options are wrong:
A. Male sex raises the population rate about fourfold but is weaker than a previous attempt as an individual predictor.
B. Unemployment is a recognised social risk factor but is weaker than a previous attempt.
D. Living alone reflects social isolation, a moderate risk factor, not the strongest one.
Where to revise: Study PDF: "Suicide: Ask, Assess, Keep Safe" (KnowMed), page 4: Risk factors and protective factors; page 3: Numbers you must know
During a flight, a 26-year-old woman eats a snack containing cashew nuts. Within 10 minutes she has generalised urticaria, lip swelling, a hoarse voice and wheeze. Her BP is 82/50 mmHg. She has no auto-injector with her. The emergency medical kit is opened. What is the most appropriate immediate treatment?
Rationale
Rapid onset of skin features with airway involvement (lip swelling, hoarseness), bronchospasm and hypotension after a known trigger is anaphylaxis. Intramuscular adrenaline is the first and most important treatment; the adult dose is 0.5 mg of 1 mg/mL (1:1000) solution into the anterolateral thigh, repeated every 5 minutes if there is no improvement. Aircraft emergency kits carry adrenaline 1 mg/mL. She should lie flat with legs raised (or sit up if breathing is difficult), receive high-flow oxygen and IV fluids if available, and the crew should involve ground-based medical support and consider diversion. Antihistamines and steroids are adjuncts only and do not treat airway obstruction or shock. The exam trap is giving undiluted IV adrenaline at the cardiac arrest dose to a patient with a pulse, which can cause fatal arrhythmias.
Why the other options are wrong:
B. Antihistamines do not reverse airway oedema, bronchospasm or shock.
C. Steroids act too slowly and are not first-line.
D. A 1 mg IV bolus is the cardiac arrest dose and is dangerous in a patient with a pulse.
Where to revise: Study PDF: "Fitness to Fly: Clearance and Inflight Emergencies" (KnowMed), page 13: Treat in the aisle; page 11: How common and what happens?
A healthy 2-month-old baby attends for routine vaccines. His 6-year-old sister is receiving chemotherapy for acute lymphoblastic leukaemia and lives in the same house. Which vaccine should be avoided for the baby?
Rationale
Household contacts of immunosuppressed people should be fully vaccinated, because this protects the vulnerable person (cocooning). Inactivated vaccines pose no risk. Among live vaccines, MMR, varicella and rotavirus can all be given to contacts: MMR virus is not transmitted, varicella vaccine virus is rarely transmitted (only if the vaccinee develops a rash, who should then avoid contact), and rotavirus vaccine virus shed in stool is managed with careful hand hygiene and nappy handling. Oral polio vaccine is the exception: vaccine virus is shed in stool for weeks and can cause vaccine-associated paralytic polio in an immunocompromised contact. The DHA guideline states that OPV should not be given to a child living with someone with impaired immunity; IPV (already in the hexavalent vaccine) is used instead.
Why the other options are wrong:
A. The hexavalent vaccine is inactivated and safe.
C. Rotavirus vaccine is allowed for contacts of immunosuppressed people, with hand hygiene after nappy changes.
D. PCV is an inactivated conjugate vaccine and safe.
Where to revise: Study PDF: "Vaccination: Schedule, Safety and Special Cases" (KnowMed), page 9: Steroids, chemotherapy, HIV and asplenia; page 7: False contraindications
On a flight from Dubai, the crew ask whether there is a doctor on board for a passenger who has collapsed. You are a GP and have had two glasses of wine with dinner, but you feel clear-headed. What is the most appropriate action?
Rationale
Professional codes (for example the GMC and equivalent standards applied by UAE regulators) expect doctors to offer help in an emergency, taking account of their own safety, competence and the availability of other options. Honesty about any factor that could affect performance, such as alcohol, lets the crew and ground-based physician judge how best to use your help, and other volunteers may be available. You should act only within your competence, obtain consent where possible, use the kit with the crew, follow ground-based medical advice, and document your findings and treatment. The captain retains overall authority, including the decision to divert. In practice, legal action against in-flight volunteers is very rare, and laws such as the US Aviation Medical Assistance Act 1998 protect volunteers except for gross negligence or wilful misconduct. The exam trap is choosing to stay silent, or to hide the alcohol.
Why the other options are wrong:
B. Modest alcohol intake does not automatically prevent useful help when declared honestly.
C. Concealing alcohol is dishonest and unsafe.
D. Delaying emergency help for indemnity is not ethical practice.
Where to revise: Study PDF: "Fitness to Fly: Clearance and Inflight Emergencies" (KnowMed), page 14: Good Samaritan duties and liability; page 12: "Is there a doctor on board?" A stepwise approach
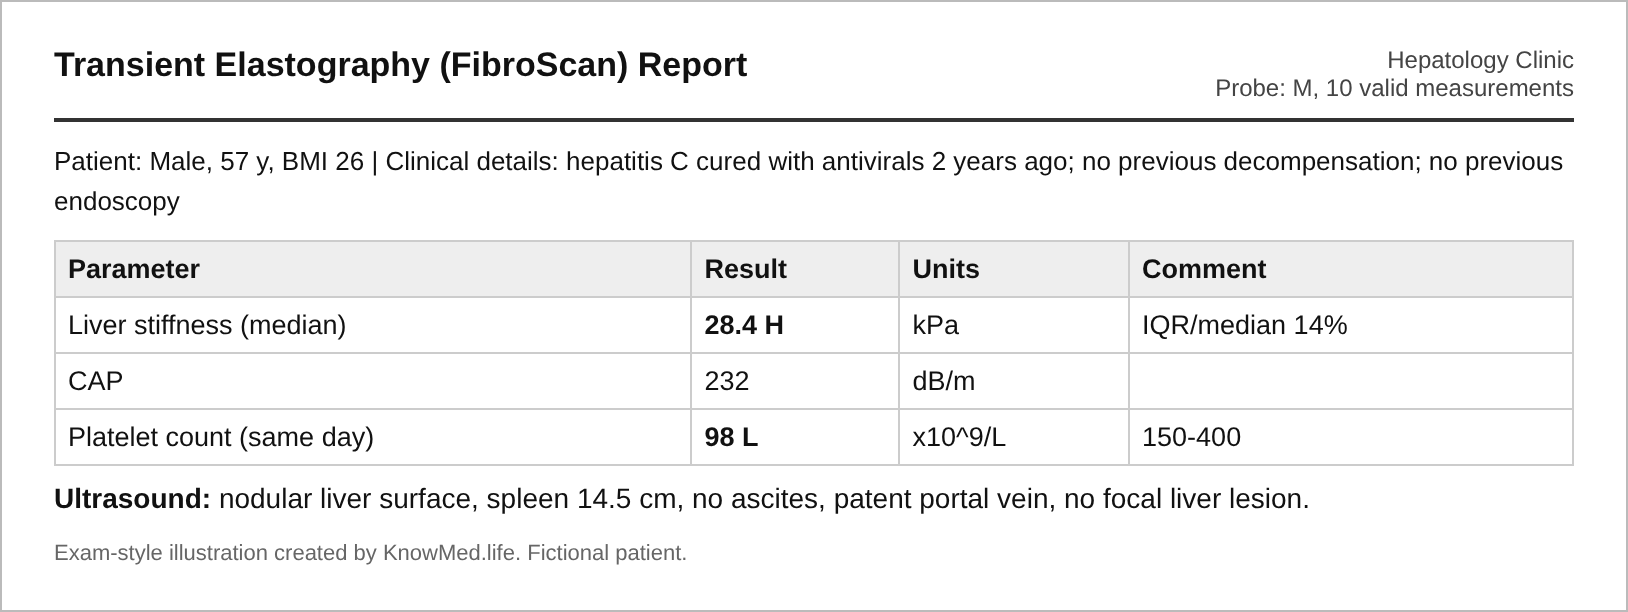
A 57-year-old man whose hepatitis C was cured 2 years ago attends for review. He has never decompensated and has never had an endoscopy. His FibroScan report is shown. Blood pressure is 128/80 mmHg and heart rate 78/min. What is the most appropriate next step?
Rationale
Under Baveno VII, a liver stiffness of 25 kPa or more in compensated advanced chronic liver disease rules in clinically significant portal hypertension (CSPH, HVPG 10 mmHg or more); his reading is 28.4 kPa with low platelets and splenomegaly. Patients with CSPH should start a non-selective beta- blocker, preferably carvedilol (6.25 mg once daily, increased to 6.25 mg twice daily after 3 days if blood pressure allows). NSBB therapy in CSPH lowers the risk of decompensation, mainly ascites, as shown in the PREDESCI trial. A patient who is taking carvedilol for CSPH does not need a screening endoscopy because the result would not change treatment. He also needs 6-monthly ultrasound surveillance for HCC, because HCC risk remains after HCV cure. Biopsy is not required when non-invasive tests are diagnostic.
Why the other options are wrong:
A. Waiting ignores CSPH, which carries a real risk of first decompensation and bleeding.
B. Elastography with platelets and ultrasound is enough; biopsy is invasive and unnecessary here.
D. Combining an NSBB with banding is for secondary prophylaxis after a bleed, not primary prophylaxis.
Where to revise: Study PDF: "Cirrhosis: From Fibrosis to Decompensation" (KnowMed), page 10: Preventing the first bleed: carvedilol - Same PDF, page 5: Baveno VII rule of five callout
A doctor is about to tell a 47-year-old woman that her biopsy shows ovarian cancer. She has arranged a quiet room, switched off her phone and invited the patient's husband as the patient requested. Using the SPIKES protocol, what should she do next?
Rationale
SPIKES is a six-step protocol for breaking bad news: Setting, Perception, Invitation, Knowledge, Emotions and Strategy/Summary. The doctor has completed the Setting step (private room, no interruptions, the person the patient wants present). The next step is Perception: asking open questions about what the patient already knows or suspects, which allows the doctor to correct misunderstandings and pitch the news at the right level. Invitation (how much she wants to know) follows, then Knowledge with a warning shot and plain language, then responding to Emotions with empathy and pauses, and finally a Strategy and summary with follow-up. This structured approach is tested frequently in UAE exams. The exam trap is jumping straight to the diagnosis.
Why the other options are wrong:
A. Delivering the news without first establishing perception and invitation risks overwhelming the patient.
C. Detailed treatment planning comes at the end (Strategy), after the news and emotions have been addressed.
D. The patient chose to have her husband present; asking him to leave disregards her wishes.
Where to revise: Study PDF: "End-of-Life Issues: Ethics, Law and UAE Practice" (KnowMed), page 5: Breaking bad news: SPIKES and truth-telling
At a family gathering in Al Ain, several children and adults develop severe vomiting and abdominal cramps about 3 hours after eating cream-filled pastries that had been left out in the heat. None has fever. A 9-year-old is mildly dehydrated but tolerating sips. What is the most likely cause and management?
Rationale
Vomiting-predominant illness starting 1 to 6 hours after eating, affecting several people who shared the same food, without fever, is typical of food poisoning from a preformed toxin. Staphylococcus aureus from a food handler multiplies in cream, custard, ham or salads left at room temperature and produces a heat-stable enterotoxin; Bacillus cereus causes a similar picture after reheated fried rice. Because the toxin is already formed in the food, symptoms start quickly and resolve within 24 to 36 hours, and antibiotics are ineffective. Management is supportive with ORS and, if vomiting is troublesome, a single dose of ondansetron in children. A food-poisoning cluster should be reported to the public health and municipality food-safety authorities. The trap is to give antibiotics for a toxin-mediated illness.
Why the other options are wrong:
A. Salmonella has an incubation of 6 to 72 hours, usually causes fever and diarrhoea, and does not need antibiotics in healthy children.
C. Campylobacter incubates for 2 to 5 days and causes diarrhoea with cramps, not rapid-onset vomiting.
D. Shigella causes febrile dysentery after 1 to 3 days, not vomiting a few hours after a meal.
Where to revise: Study PDF: "Bacterial Gastroenteritis in Children: The Dehydration and Dysentery Pathway" (KnowMed), page 3: The bacterial line-up: source, incubation, clue - Same PDF, page 10: Zinc, antiemetics and what to avoid
Under UAE Federal Decree-Law No. 10 of 2022, what is the penalty for deliberately entering false information in a death record?
Rationale
Article 25 of Federal Decree-Law No. 10 of 2022 on the registration of births and deaths punishes anyone who deliberately submits incorrect data for a death record, changes records without a final court ruling, or destroys or loses a death record, with imprisonment of not less than one year and a fine of AED 100,000-500,000, or one of these penalties. Article 23 separately fines anyone who learns of a death through kinship or work and deliberately fails to report it, up to AED 15,000. Article 26 adds that harsher penalties under other laws, such as forgery, still apply, and professional sanctions may follow. Exams often frame this as a family asking the doctor to change the cause of death: the correct answer is always to refuse politely, record the truth and explain.
Why the other options are wrong:
A. A warning is not the legal penalty for deliberate falsification.
C. AED 5,000 relates to failing to notify a birth under the same law, not falsifying a death record.
D. A short suspension alone is not the penalty set by the decree-law.
Where to revise: Study PDF: "Death Certificate: Certify, Refer, Register" (KnowMed), page 12: Honesty, families and the UAE penalties
A 68-year-old man with long-standing COPD reports 2 months of increasing ankle swelling. He has a raised JVP, a loud P2, a left parasternal heave and pitting oedema to the knees. Chest examination shows hyperinflation without crackles. His ECG is shown. What is the most likely cause of his oedema?
Rationale
The ECG shows tall peaked P waves in II, III and aVF (P pulmonale, right atrial enlargement), right axis deviation (negative QRS in I, positive in III and aVF), a dominant R wave in V1 and T-wave inversion in V1-V2 (right ventricular strain). Together with a raised JVP, loud P2 and parasternal heave this indicates right ventricular hypertrophy from pulmonary hypertension caused by chronic hypoxia in COPD. Chronic alveolar hypoxia causes pulmonary vasoconstriction and vascular remodelling, increasing right ventricular afterload. Management includes treating hypoxaemia (LTOT if criteria are met), diuretics for oedema and optimising COPD therapy. Echocardiography confirms raised pulmonary pressures and right ventricular dilatation. The trap is labelling the oedema as left heart failure when the ECG shows right-sided changes and the lungs have no crackles.
Why the other options are wrong:
A. An old anterior MI would leave Q waves in V1-V4 and left-sided signs; the ECG shows right-sided strain.
B. Nephrotic syndrome causes oedema with a normal JVP and heavy proteinuria, not a loud P2 and heave.
D. Calcium-channel blocker oedema does not raise the JVP or cause right ventricular strain on the ECG.
Where to revise: Study PDF: "AECOPD: The Acute Exacerbation Pathway" (KnowMed), page 11: Complications and special situations - Study PDF: "COPD: The Stable Disease Pathway" (KnowMed), page 14: Complications and comorbidities
A 50-year-old man with severe depression has been tearful and withdrawn for 3 months. His wife reports that over the last 2 days he has suddenly become calm and cheerful, has visited old friends to say how much they mean to him and has given his watch collection to his son. What is the most likely explanation?
Rationale
A sudden calm after a long period of severe depression, combined with saying goodbye and giving away valued possessions, is a classic warning sign that the person has made a decision to die and feels relief. These are preparatory behaviours on the suicidal spectrum. The correct response is a same- day assessment asking directly about thoughts, plan, intent, means and preparations, with collateral history from his wife. If plan and intent are present he must not be left alone and needs emergency psychiatric assessment; means such as stored medicines should be removed. Antidepressants take 2-4 weeks to improve mood, and energy may return before mood, which can itself raise risk early in treatment. The exam trap is reading the change as recovery.
Why the other options are wrong:
A. Spontaneous recovery does not happen over 2 days and does not explain goodbye visits and giving away possessions.
B. Antidepressant benefit takes weeks; a 2-day "response" with farewell behaviour is a red flag, not improvement.
C. Hypomania causes elevated or irritable mood, increased energy and activity, not quiet farewells.
Where to revise: Study PDF: "Suicide: Ask, Assess, Keep Safe" (KnowMed), page 5: Warning signs and myths
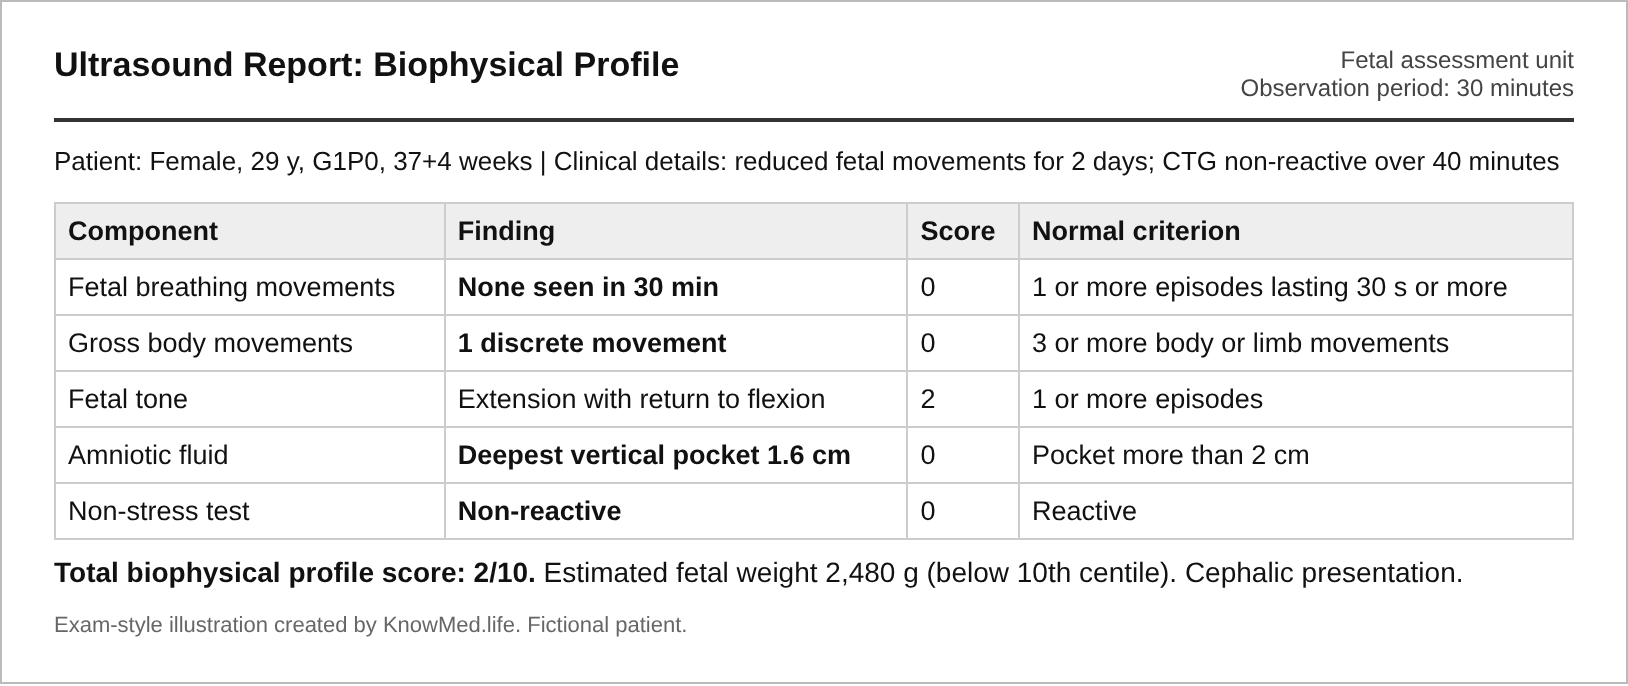
A 29-year-old primigravida at 37+4 weeks presents with reduced fetal movements for 2 days. Her CTG is non-reactive over 40 minutes and the biophysical profile is shown. What is the most appropriate management?
Rationale
The biophysical profile scores 2/10: no breathing movements, only one body movement, a deepest pool of 1.6 cm (oligohydramnios) and a non-reactive NST, with only tone preserved. A BPP of 4 or less suggests fetal hypoxia, and oligohydramnios reflects chronic placental insufficiency, supported here by an estimated fetal weight below the 10th centile. At term (37+4 weeks) with an abnormal BPP, the baby is safer delivered than in utero. The mode of delivery depends on the clinical picture and CTG; many such fetuses do not tolerate labour. Recurrent reduced movements at term are themselves a reason to discuss delivery.
Why the other options are wrong:
A. Waiting a week with a BPP of 2/10 risks stillbirth.
B. Kick charts are not recommended, and this fetus has objective evidence of compromise.
C. Repeating in 24 hours is for an equivocal BPP of 6; this score is 2.
Where to revise: Study PDF: "Prenatal Care: Book, Screen, Protect" (KnowMed), page 11: NST, biophysical profile and Doppler; page 12: Reduced fetal movements pathway
A 6-week-old girl of Emirati parents attends for her routine check in a primary care centre. The doctor notices a 6 cm flat, uniform blue-grey patch over the sacrum and buttocks. The mother says it has been present since birth and has not changed. The baby is thriving and there are no other findings. What is the most appropriate action?
Rationale
A flat, uniform blue-grey patch over the sacrum and buttocks that has been present since birth and does not change over days is congenital dermal melanocytosis (Mongolian spot). It is very common in babies of Arab, Asian and African descent and usually fades during childhood. Unlike a bruise, it is not tender, does not swell and does not change colour over a few days. It is one of the most common mimics of bruising, so documenting it clearly in the record (including a body map) protects the family from later misunderstanding. No investigation is needed. If there is doubt, review after a few days: a bruise changes, a melanocytic patch does not.
Why the other options are wrong:
A. A congenital, unchanging blue-grey patch is not a bruise and does not need a child protection work-up.
B. There is no bruising or bleeding to investigate.
C. Dermal melanocytosis fades spontaneously and does not need treatment.
Where to revise: Study PDF: "Child Maltreatment: Recognise, Protect, Report" (KnowMed), page 10: The mimics of abuse
A 33-year-old woman with a known placenta praevia has a second episode of moderate bleeding at 35+2 weeks. It has now settled and the team plans a caesarean section in the next few days. She has not received corticosteroids before. Which regimen should be considered to reduce neonatal respiratory morbidity?
Rationale
Antenatal corticosteroids accelerate fetal lung maturation by stimulating surfactant production and reduce respiratory distress syndrome, intraventricular haemorrhage and neonatal death. NICE NG25 says to offer them from 24+0 to 33+6 weeks and to consider them from 34+0 to 35+6 weeks when preterm birth is likely; RCOG Green-top Guideline 27a advises a single course at 34+0 to 35+6 weeks for women with praevia or low-lying placenta. The standard course is betamethasone 12 mg IM, two doses 24 hours apart (or dexamethasone 6 mg IM, four doses 12 hours apart); maximal benefit is seen when birth occurs between 24 hours and 7 days after the first dose. With a bleeding history, RCOG suggests delivery at 34+0 to 36+6 weeks. Prednisolone and hydrocortisone are largely inactivated by the placenta and do not reach the fetus in useful amounts.
Why the other options are wrong:
A. Oral dexamethasone and a single dose are not the recommended regimen.
B. Hydrocortisone is metabolised by placental 11-beta-hydroxysteroid dehydrogenase and does not mature the fetal lungs.
C. Prednisolone also crosses the placenta poorly and is not used for fetal lung maturation.
Where to revise: Study PDF: "Antepartum Haemorrhage: Previa, Abruption and Beyond" (KnowMed), page 11: Drugs you must dose correctly; page 12: When and how to deliver
A 22-year-old university student in Dubai with more severe depression starts sertraline 50 mg daily alongside CBT. She has no current suicidal thoughts. When should she be reviewed after starting the antidepressant?
Rationale
Antidepressants have been associated with a small increase in suicidal thoughts and behaviour early in treatment in children, adolescents and young adults under 25. NICE NG222 therefore recommends that people aged 18-25, and anyone at particular risk of suicide, are reviewed within 1 week of starting an antidepressant; others are reviewed within 2-4 weeks. At review, check side effects (nausea, anxiety, agitation, sexual dysfunction), adherence and suicidal ideation, and give crisis contacts (UAE emergency 998). Benefit may appear in 1-2 weeks, but full effect takes 4-6 weeks. At-risk patients should be prescribed smaller quantities.
Why the other options are wrong:
B. 2-4 weeks is the usual review for adults over 25 without suicide risk.
C. 4-6 weeks is when lack of response is judged, not the first review.
D. Waiting 3 months is unsafe at the start of treatment.
Where to revise: Study PDF: "Major Depressive Disorder: Diagnose, Treat, Keep Safe" (KnowMed), page 8: NICE NG222 stepped-care algorithm; page 10: SSRI side effects and serotonin syndrome
A 52-year-old woman recovering from her first episode of uncomplicated diverticulitis asks what she should eat to reduce her risk of another attack. Which advice is correct?
Rationale
NICE NG147 and the AGA advise a healthy balanced diet rich in whole grains, fruit and vegetables, increasing fibre gradually and drinking enough fluid, with bulk-forming laxatives if constipated. Large cohort studies found no link between eating nuts, corn, popcorn or seeds and diverticulitis or bleeding; in fact nut intake was associated with lower risk. Other helpful measures are regular exercise, weight loss if overweight, stopping smoking, limiting red meat and minimising NSAID and opioid use. The benefit of fibre takes several weeks. Mesalazine, rifaximin and probiotics have not been shown to prevent recurrent diverticulitis. The traditional advice to avoid seeds is a classic exam myth.
Why the other options are wrong:
A. A low-fibre diet may be used briefly during an acute attack but long term it increases risk.
B. There is no evidence that nuts, seeds or popcorn cause diverticulitis; avoidance is unnecessary.
D. Mesalazine has not been shown to prevent recurrence of diverticulitis.
Where to revise: Study PDF: "Diverticulitis: Classify, Treat, Follow Up" (KnowMed), page 14: Lifestyle advice that prevents attacks; page 3: Who gets it and why
A 60-year-old woman is admitted with complete small bowel obstruction from adhesions. She is vomiting despite a nasogastric tube. Which antiemetic should be AVOIDED?
Rationale
Metoclopramide is a dopamine antagonist with prokinetic action that increases gastric and small bowel contraction. In complete mechanical obstruction this increases colic, vomiting and intraluminal pressure and may risk perforation, so it is contraindicated. Ondansetron (5-HT3 antagonist) and cyclizine (antihistamine) are safe choices, and haloperidol is widely used in palliative malignant bowel obstruction together with hyoscine butylbromide, octreotide and dexamethasone. The nasogastric tube remains the main treatment for vomiting in SBO. Exam trap: metoclopramide can be used in partial obstruction or gastroparesis but not in complete mechanical obstruction.
Why the other options are wrong:
A. Ondansetron has no prokinetic effect and is safe in obstruction.
B. Cyclizine is antihistaminic and antispasmodic and is commonly used in obstruction.
D. Haloperidol is an accepted antiemetic in malignant bowel obstruction.
Where to revise: Study PDF: "Bowel Obstruction: Spot, Decompress, Decide" (KnowMed), page 10: Drip, suck and the right drugs
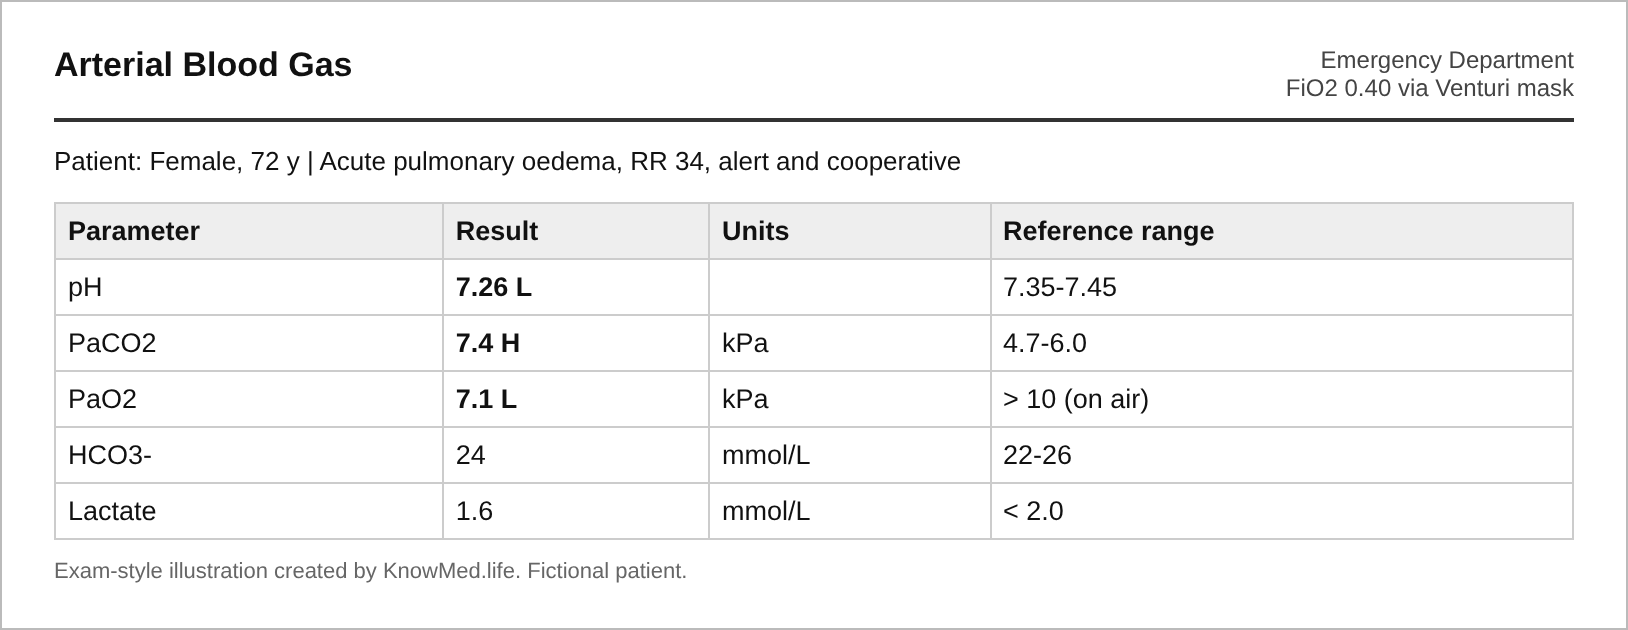
A 72-year-old woman with acute pulmonary oedema remains breathless on 40% oxygen via a Venturi mask. She is alert and cooperative, RR 34/min, BP 158/90 mmHg. Her arterial blood gas is shown. What is the most appropriate next step?
Rationale
The ABG shows acute respiratory acidosis (pH 7.26, PaCO2 7.4 kPa, normal bicarbonate) with hypoxaemia (PaO2 7.1 kPa on 40% oxygen). In acute pulmonary oedema, fatigue of respiratory muscles leads to hypercapnia. NIV is recommended for respiratory distress (RR above 25, SpO2 below 90%) and should be started as soon as possible; BiPAP is preferred when there is hypercapnia and acidosis. NIV reduces intubation rates by recruiting alveoli and reducing LV afterload. Intubation is reserved for those who fail NIV, have reduced consciousness, cannot protect the airway or are in shock. The trap is to keep increasing oxygen, which does not correct ventilatory failure.
Why the other options are wrong:
A. More oxygen will not fix hypercapnic respiratory failure and delays effective treatment.
C. Morphine depresses ventilation and worsens hypercapnia.
D. She is alert and cooperative, so NIV should be tried first.
Where to revise: Study PDF: "Acute Heart Failure: The Emergency Pathway" (KnowMed), page 8: Acute HF management algorithm; page 10: Oxygen, vasodilators and inotropes: doses
A 28-year-old man with Crohn disease in remission presents with a painful red right eye, photophobia and blurred vision for 2 days. Visual acuity is reduced and the pupil is small. What is the most appropriate action?
Rationale
Pain, photophobia, blurred vision, reduced acuity and a small pupil suggest anterior uveitis, an extraintestinal manifestation of IBD. Unlike episcleritis, erythema nodosum and peripheral arthritis, uveitis does not track bowel disease activity, so it can occur while the gut is in remission. It needs same- day slit-lamp examination; treatment is topical steroids and cycloplegics under ophthalmology, and untreated uveitis can cause synechiae, glaucoma and visual loss. Episcleritis, by contrast, is mild, usually painless or mildly uncomfortable, does not affect vision and settles with treatment of the flare. Uveitis is also linked with HLA-B27 and ankylosing spondylitis, which is more common in IBD.
Why the other options are wrong:
A. This is not conjunctivitis; reduced vision and photophobia are red flags.
C. Uveitis is independent of bowel activity.
D. The bowel is in remission; the eye needs urgent specialist treatment.
Where to revise: Study PDF: "Crohn Disease: Skip Lesions to Surgery" (KnowMed), page 5: Extraintestinal manifestations and malabsorption
A 30-year-old woman attends a pharmacy-linked clinic in Dubai 80 hours after unprotected sex on day 12 of a regular cycle. She weighs 92 kg (BMI 32) and takes no medicines. She declines an intrauterine device. What is the most appropriate emergency contraception?
Rationale
She is 80 hours after unprotected sex, near ovulation, with a BMI over 26 and weight over 70 kg, and she has declined the Cu-IUD, which would otherwise be first choice. Ulipristal acetate (a selective progesterone receptor modulator) is licensed and effective up to 120 hours and still delays ovulation closer to the LH surge, so it is more effective than levonorgestrel. Levonorgestrel is licensed up to 72 hours and appears ineffective beyond 96 hours. CoSRH advises ulipristal (or 3 mg levonorgestrel if ulipristal is unsuitable) when BMI is over 26 or weight over 70 kg. She should wait 5 days before starting hormonal contraception, and have a pregnancy test 3 weeks after the sex. Vomiting within 3 hours means the dose should be repeated.
Why the other options are wrong:
B. At 80 hours a single 1.5 mg levonorgestrel dose is outside its licence and less effective, especially with her weight.
C. Ulipristal works up to 120 hours.
D. The Yuzpe regimen is less effective, causes more nausea and is only used when nothing else is available.
Where to revise: Study PDF: "Family Planning and Emergency Contraception: Choose, Start, Rescue" (KnowMed), page 10: Three options, three time windows; page 11: Emergency contraception decision pathway
A 70-year-old man on warfarin for atrial fibrillation has had one episode of visible haematuria. His INR is 2.6 (target 2-3). Urine culture is negative and he has no pain. He asks if the warfarin is to blame. What is the most appropriate management?
Rationale
Visible haematuria in a patient whose anticoagulation is in the therapeutic range must never be blamed on the anticoagulant without investigation. Controlled anticoagulation does not by itself cause haematuria; it unmasks an underlying lesion, and studies show that anticoagulated patients have a similar rate of urological cancer to those not anticoagulated. He meets NICE NG12 criteria (aged 45 or over with unexplained visible haematuria and no UTI) for a suspected cancer pathway referral. The standard evaluation is flexible cystoscopy for the bladder plus CT urography for the kidneys and upper tracts. Anticoagulation should usually be continued if bleeding is mild and the INR is in range, because his stroke risk is significant. The trap is the reassuring explanation offered by the patient or a colleague.
Why the other options are wrong:
A. Stopping warfarin exposes him to stroke risk and does not address the cause of bleeding.
B. Haematuria is not an expected effect of a therapeutic INR and must be investigated.
D. Changing anticoagulant does not investigate a possible bladder or kidney cancer.
Where to revise: Study PDF: "Haematuria: From Dipstick to Cystoscopy" (KnowMed), page 5: Clues that point to the cause (Never box); page 8: Risk-based referral: NICE NG12 and AUA 2025; page 12: Children, pregnancy and other groups
A 21-year-old soldier with exertional heatstroke is being cooled by ice-water immersion. His rectal temperature was 41.8 C on arrival and is now falling steadily. At what rectal temperature should active immersion cooling be stopped?
Rationale
Active cooling is stopped at about 38.5-39 C because the core temperature continues to fall after the patient is removed from the water (afterdrop). Cooling to 37 C risks overshoot hypothermia, arrhythmia and shivering, which generates heat. Stopping too early, at 40-41 C, leaves the patient in the damaging hyperthermic range. Rectal (or oesophageal) temperature should be monitored continuously throughout cooling, then every 15-30 minutes afterwards to detect rebound hyperthermia. The aim is to reach this endpoint within 30 minutes of collapse.
Why the other options are wrong:
A. 41.0 C is still severe hyperthermia; stopping here allows ongoing organ injury.
B. 40.0 C is the diagnostic threshold of heatstroke, not a safe endpoint.
C. Cooling to 37 C causes overshoot hypothermia because of afterdrop.
Where to revise: Study PDF: "Heatstroke: Cool First, Transport Second" (KnowMed), page 9: Heatstroke management algorithm; page 10: Cooling methods ranked by speed
At 07:30 you notice that a senior surgical colleague, due to operate at 08:00, smells strongly of alcohol, is slurring his words and is unsteady. What is the most appropriate action?
Rationale
Patient safety overrides hierarchy and loyalty to colleagues. A doctor who appears intoxicated must not treat patients, so the immediate priority is to prevent him operating and to escalate at once to the clinical lead, head of department or medical director, who can arrange cover and support. Speaking to him privately and respectfully preserves dignity and may allow him to step back voluntarily. Impairment may reflect an illness such as alcohol use disorder, so the response should combine safety with support and referral to occupational health. The incident should be documented and reported through the facility's process. The trap is either silence because of seniority or a public confrontation.
Why the other options are wrong:
A. Silence puts patients at risk and is itself a breach of professional duty.
B. A public confrontation humiliates the colleague and may escalate the situation, while not ensuring safety.
D. Waiting until after the list allows him to operate while impaired.
Where to revise: Study PDF: "Communication During Residency: Breaking Bad News and Beyond" (KnowMed), page 13: Anger, conflict and speaking up
A 48-year-old man originally from southern China, working in Dubai, has had a blocked feeling and reduced hearing in his right ear for 2 months. He has no ear pain. Otoscopy shows a dull, retracted right drum with an air-fluid level; the left ear is normal. Tympanometry is type B on the right. What is the most important next step?
Rationale
Persistent unilateral otitis media with effusion is uncommon in adults and should raise suspicion of a mass obstructing the Eustachian tube opening in the nasopharynx. Nasopharyngeal carcinoma is particularly common in people from southern China and South-East Asia and is associated with Epstein-Barr virus. The key step is ENT referral for nasendoscopy of the postnasal space, with biopsy of any lesion and imaging if needed; palpation of the neck for nodes is also essential. Antibiotics or steroids may falsely reassure while a malignancy progresses. A grommet may later be placed for symptoms, but only after the nasopharynx has been examined. The exam trap is treating adult unilateral glue ear exactly as in a child.
Why the other options are wrong:
A. There is no acute infection, and antibiotics do not clear effusion.
B. Medical treatment delays the essential exclusion of a nasopharyngeal tumour.
D. Inserting a grommet first would miss the underlying cause.
Where to revise: Study PDF: "Acute Otitis Media: Diagnose, Treat or Watch" (KnowMed), page 4: Clinical features by age; page 13: Neonates, perforation, adults and flying
A 52-year-old woman has had painful swollen hands and long morning stiffness for 4 years and has never been treated. Her hand X-ray report is shown. What is the most likely diagnosis?
Rationale
The report describes symmetrical periarticular osteopenia, uniform joint-space narrowing and marginal erosions at the MCP joints, wrists and ulnar styloids, soft-tissue swelling and early ulnar deviation, with normal DIP joints. These are the classic radiographic features of RA, remembered by the mnemonic LESS: loss of joint space, erosions, soft-tissue swelling and soft bones (osteopenia). Marginal 'bare area' erosions occur where synovium touches bone not covered by cartilage. The absence of osteophytes, periosteal new bone and tophi argues against the other arthritides. NICE recommends X- rays of the hands and feet at diagnosis because erosions predict progression. Erosions after years of untreated disease show why early DMARD treatment matters.
Why the other options are wrong:
A. Osteoarthritis affects the DIP and PIP joints with osteophytes and subchondral sclerosis, not osteopenia and marginal erosions.
B. Psoriatic arthritis favours the DIP joints, is often asymmetric and shows periosteal new bone and pencil-in-cup deformity.
C. Gout shows punched-out erosions with overhanging edges and soft-tissue tophi, usually with preserved bone density.
Where to revise: Study PDF: "Rheumatoid Arthritis: From Synovitis to Treat-to-Target" (KnowMed), page 5: Serology, inflammation and imaging; page 7: RA versus the look-alikes
A 36-year-old man with cellulitis of the forearm on day 1 of IV antibiotics decides, with capacity, to leave against medical advice after a full discussion. Which of the following should be done before he leaves?
Rationale
Once a competent patient has chosen to leave, the goal is harm reduction: the best care he will accept. This includes an oral antibiotic course (for example flucloxacillin or another agent covering streptococci and Staphylococcus aureus), an early review appointment, a plan for pending results, a written discharge summary and clear advice on warning symptoms such as spreading redness, fever or rigors. He should be told he can return at any time and given the number to call or advised to dial 998. The IV cannula must be removed to prevent line infection or misuse. Leaving against advice ends the admission but not the duty of care, and withholding treatment as punishment is unethical.
Why the other options are wrong:
B. Withholding antibiotics punishes the patient and increases the risk of sepsis.
C. The duty of care continues; a discharge summary and follow-up are still needed.
D. Making departure conditional on payment is coercive.
Where to revise: Study PDF: "DAMA: Discharge Against Medical Advice" (KnowMed), page 10: Harm reduction: the best care he will accept
A 63-year-old woman with CKD G4 who takes ramipril and spironolactone presents with generalised weakness. Serum potassium is 7.1 mmol/L. She is haemodynamically stable. Her ECG is shown. What is the most appropriate immediate treatment?
Rationale
The ECG shows tall, narrow, peaked (tented) T waves, most marked in V2-V4, with flattened, almost absent P waves: classic changes of severe hyperkalaemia. With potassium above 6.5 mmol/L or any ECG change, the first step is IV calcium (10% calcium gluconate, 10-30 mL over 5-10 minutes, repeated if ECG changes persist), which stabilises the cardiac membrane within minutes but does not lower potassium. Next, potassium is shifted into cells with insulin 10 units plus 25 g glucose IV and salbutamol 10-20 mg nebulised, followed by removal with a binder, diuretics if not oliguric, or dialysis if refractory. Ramipril and spironolactone should be stopped, and nephrotoxic or potassium-raising drugs reviewed. Untreated, the ECG progresses to broad QRS, sine-wave pattern, ventricular fibrillation or asystole. The trap is choosing a potassium-lowering treatment first while the heart is unprotected.
Why the other options are wrong:
B. Potassium binders act over hours and are used after emergency stabilisation, not alone.
C. Furosemide is slow and unreliable in advanced CKD and does not protect the myocardium.
D. Refractory severe hyperkalaemia needs urgent, not elective, dialysis.
Where to revise: Study PDF: "Chronic Kidney Disease: Stage, Protect, Prepare" (KnowMed), page 12: Potassium, fluid, heart and drug safety; page 13: Refer, plan and replace kidney function
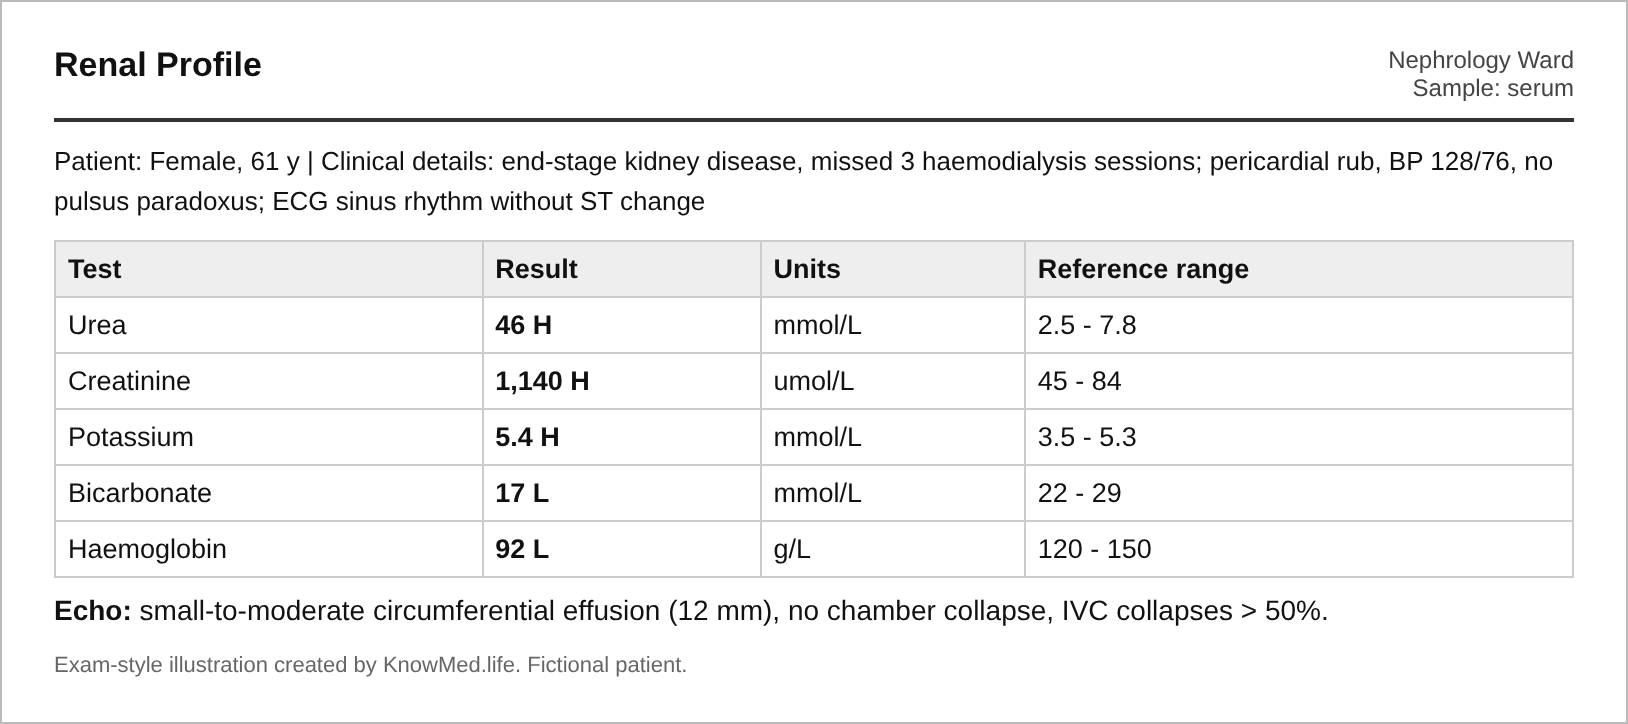
A 61-year-old woman with end-stage kidney disease missed 3 dialysis sessions. She has pleuritic chest pain and a pericardial rub. She is haemodynamically stable with no pulsus paradoxus, and her ECG shows no ST change. Her results are shown. Uraemic pericarditis is diagnosed. Which approach to dialysis is most appropriate?
Rationale
The report shows marked uraemia (urea 46 mmol/L) with a small-to-moderate effusion but no tamponade. Uraemic pericarditis is caused by retained toxins and typically lacks the classic ECG changes because the myocardium is not inflamed. The treatment is to intensify dialysis, often daily for 1-2 weeks, which resolves most cases. Heparin should be minimised or avoided because uraemic pericarditis is often haemorrhagic and anticoagulation increases the risk of haemopericardium and tamponade. If the effusion enlarges or tamponade develops, drainage is needed; NSAIDs are of limited benefit and colchicine requires dose caution in kidney failure.
Why the other options are wrong:
A. Stopping dialysis worsens uraemia, the cause of the pericarditis.
B. Usual-frequency dialysis has already failed to control uraemia and full heparin raises the bleeding risk.
C. Switching modality is not first-line; more intensive haemodialysis is the standard approach.
Where to revise: Study PDF: "Pericarditis: The Pleuritic Chest Pain Pathway" (KnowMed), page 11: Specific pericarditis syndromes; page 16: Golden rules for MCQs
A 15-year-old girl in Al Ain has moderate to severe depression. She has had 6 sessions of individual CBT without improvement, and there is no suicidal intent. A child and adolescent psychiatrist reviews her. What is the most appropriate medication?
Rationale
In children and young people, psychological therapy is first-line. NICE NG134 recommends that if moderate to severe depression does not respond after 4-6 sessions, a specialist may offer fluoxetine in combination with psychological therapy. Fluoxetine has the best evidence in this age group: start at 10 mg daily and increase to 20 mg after 1 week if needed. Sertraline or citalopram are second-line options if fluoxetine fails. Under-25s need close monitoring for suicidal thoughts, agitation and self-harm, usually weekly at first. Irritability may replace low mood in adolescents.
Why the other options are wrong:
A. Sertraline is second-line in adolescents, and medication should be combined with therapy.
C. Tricyclics are ineffective in young people and dangerous in overdose.
D. Venlafaxine is not recommended in under-18s because of increased suicidality signals.
Where to revise: Study PDF: "Major Depressive Disorder: Diagnose, Treat, Keep Safe" (KnowMed), page 12: Adolescents, pregnancy and older adults
A 47-year-old man is starting apixaban for a provoked proximal DVT. He asks whether he should wear elastic graduated compression stockings to stop the leg problems that his father developed after a clot. What is the most accurate advice according to NICE?
Rationale
Post-thrombotic syndrome causes chronic leg pain, heaviness, swelling, pigmentation and venous ulcers in 20-50% of people after DVT, especially after proximal or recurrent DVT. Older trials suggested stockings prevented it, but the larger SOX trial showed no benefit, so NICE NG158 advises not offering elastic graduated compression stockings to prevent post-thrombotic syndrome or VTE recurrence. Stockings can still be used to manage leg symptoms, with advice on how to wear and replace them. Before any compression, peripheral arterial disease should be excluded because compression can cause ischaemia. Staying active and adequate early anticoagulation are the measures that reduce post- thrombotic syndrome risk. The trap is the outdated advice to wear stockings for 2 years.
Why the other options are wrong:
A. This was older advice; current NICE guidance does not recommend stockings for prevention.
C. Stockings never replace anticoagulation for a proximal DVT.
D. An ABPI below 0.5 indicates severe arterial disease, which is a contraindication to compression, not an indication.
Where to revise: Study PDF: "Deep Vein Thrombosis: From Swollen Leg to Anticoagulation" (KnowMed), page 11: Filters, thrombolysis, stockings and odd-site clots; page 12: PE, post-thrombotic syndrome, HIT and bleeding
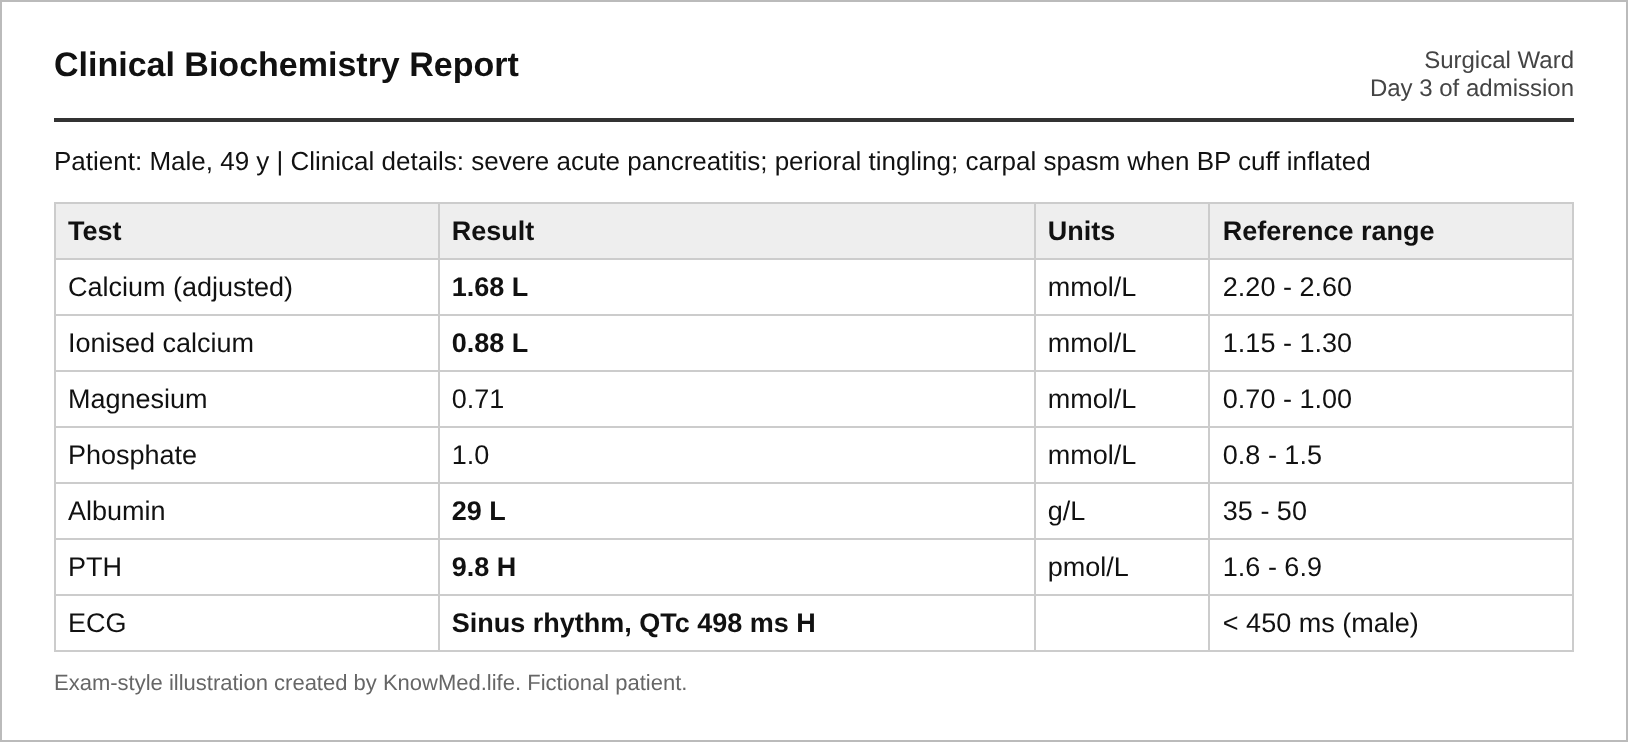
A 49-year-old man on day 3 of severe acute pancreatitis complains of perioral tingling. Carpal spasm occurs when a blood pressure cuff is inflated. His results are shown. What is the main mechanism of this abnormality?
Rationale
The report shows true hypocalcaemia: adjusted calcium 1.68 mmol/L and ionised calcium 0.88 mmol/L, with QTc prolongation and a positive Trousseau sign. In acute pancreatitis, lipase released into peripancreatic fat produces free fatty acids that bind calcium (saponification), lowering serum calcium. PTH is appropriately raised and magnesium is normal, so the parathyroid response is intact. Hypocalcaemia below 2 mmol/L is a marker of severity in the Glasgow-Imrie score. Symptomatic hypocalcaemia with tetany or a long QT is treated with IV calcium gluconate (10 mL of 10% over about 10 minutes) with ECG monitoring, and magnesium is corrected if low. The trap is treating a low total calcium caused only by low albumin; here the ionised calcium confirms true hypocalcaemia.
Why the other options are wrong:
A. PTH is raised, not low, so the parathyroids are responding normally.
C. Magnesium is within the normal range.
D. There is no history of loop diuretic use, and loop diuretics are not the mechanism in pancreatitis.
Where to revise: Study PDF: "Acute Pancreatitis: From Lipase to Necrosis" (KnowMed), page 4: Presentation and classic traps; page 14: Systemic and late complications
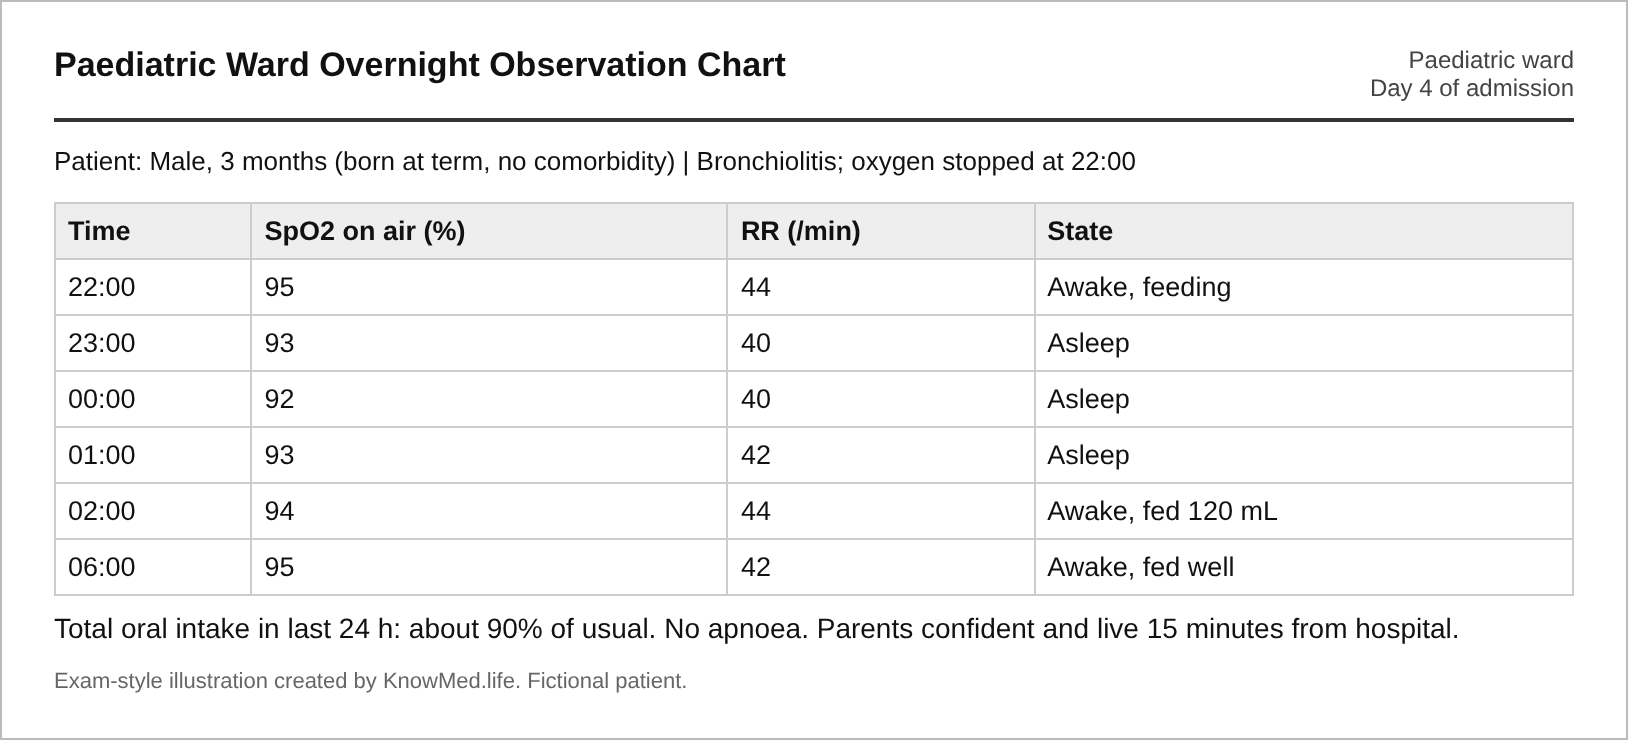
A 3-month-old boy born at term with no comorbidity was admitted 4 days ago with bronchiolitis. Oxygen was stopped at 22:00. His overnight observation chart is shown. He still has a cough. What is the most appropriate plan?
Rationale
The chart shows 8 hours off oxygen with SpO2 of 92-95% on air, including several hours asleep, a stable respiratory rate, no apnoea and oral intake of about 90% of usual. NICE discharge criteria are clinical stability, adequate oral intake and SpO2 maintained above 90% (for children 6 weeks and over without comorbidity) for 4 hours including a period of sleep, together with confident carers. He meets all of these. Cough commonly persists for up to 3 weeks and is not a reason to stay in hospital. Parents should be told the red flags: worsening breathing, intake 50-75% of normal or no wet nappy for 12 hours, apnoea or cyanosis, and exhaustion, and to avoid smoking at home. The trap is keeping children in for normal sleep dips or a lingering cough.
Why the other options are wrong:
A. Saturations of 92% are above his 90% threshold; restarting oxygen only prolongs admission.
B. A target of 95% or more is not required and is not evidence based.
C. Cough lasts up to 3 weeks in many children and does not delay discharge.
Where to revise: Study PDF: "Bronchiolitis: Wheezy Infant to Safe Discharge" (KnowMed), page 9: Oxygen and admission thresholds; page 15: Sending them home safely